Chronic Lyme – A review

In my last post, I raised the question whether chronic Lyme is often a false positive to re-activated EBV and/or CMV and/or other Herpes virus (due to microbiome shifts). I beleive that Post Infection Fatigue Syndrome is a better approach for treatment success. It is a question that needs to be asked if you have a chronic Lyme diagnosis.

  • “False-positive results of serological tests for Lyme disease have been reported in cases of recent primary infection with varicella-zoster virus [1,2], Epstein-Barr virus [3,4], and cytomegalovirus [3]. We report the first association of false-positive results of serological testing for Lyme disease with infection due to another of the herpesviruses, herpes simplex virus (HSV) type 2.” [2005]

Reviewing PubMed, I found the following for your consideration

  • “Post-treatment Lyme disease symptoms (PTLDS) and myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) have several clinical features in common, including fatigue, musculoskeletal pain, and cognitive difficulties (Gaudino et al., 1997). Immunologic mechanisms have been suspected to play a role in both PTLDS and ME/CFS. However, biomarkers for the two conditions are currently lacking, creating a barrier to better understand them.” [2015]
  • Living in Limbo: Contested Narratives of Patients With Chronic Symptoms Following Lyme Disease. [2015]
  • “Six months after completion of therapy, Lyme disease patients were found to have 31 to 60% of their pathways in common with three different immune-mediated chronic diseases. No differential gene expression signature was observed between Lyme disease patients with resolved illness to those with persistent symptoms at 6 months post-treatment” [2016] – this symptomless post treatment and persistent symptoms have the same gene expression — implying that it is not a persistent lyme bacteria!
  • “The attribution of chronic, non-specific symptoms to “chronic Lyme disease”, in the absence of specific evidence of ongoing B. burgdorferi infection, is inappropriate and unfortunate, leading not only to unneeded treatment and its associated complications, but also to missed opportunities for more appropriate management of patients’ often disabling symptoms.” [2016]
  • “Lyme“: Chronic Fatigue Syndrome by Another Name? [2016]
  • Subjective health complaints are not associated with tick bites or antibodies to Borrelia burgdorferi sensu lato in blood donors in western Norway: a cross-sectional study. [2015]
  • “Patients with persistent symptoms possibly associated with Lyme disease often provide a challenge for clinicians. Recent studies have provided additional evidence that viable B. burgdorferi do not persist after conventional treatment with antimicrobials, indicating that ongoing symptoms in patients who received conventional treatment for Lyme disease should not be attributed to persistent active infection.” [2015]
  • Lyme Disease Diagnosed by Alternative Methods: A Phenotype Similar to That of Chronic Fatigue Syndrome. [2015]
  • ” When these symptoms occur in patients with Lyme disease, they typically also subside after antimicrobial treatment, although this may take time. Chronic fatigue states have been reported to occur following any number of infections, including Lyme disease. The mechanism underlying this association is unclear, although there is no evidence in any of these infections that these chronic post treatment symptoms are attributable to ongoing infection with B. burgdorferi or any other identified organism. Available appropriately controlled studies indicate that additional or prolonged courses of antimicrobial therapy do not benefit patients with a chronic fatigue-like state after appropriately treated Lyme disease.” [2015]
  • ” Data do not support the proposition that chronic, treatment-refractory infection with Borrelia burgdorferi is responsible for the many conditions that get labeled as chronic Lyme disease. Prolonged symptoms after successful treatment of Lyme disease are uncommon, but in rare cases may be severe. Prolonged courses of antibiotics neither prevent nor ameliorate these symptoms and are associated with considerable harm.” [2015]

Many of researchers of the papers above were actively (optimistically!) looking for alternative evidence that Borrelia burgdorferi was still a player with Chronic Lyme. My read is simple, there is no clean evidence to deem Chronic Lyme to be different in any way the ME/CFS.  Most people have had one or more herpes virus in their life, a virus that can be re-activated and result in (false-)positive lab report for the classic Lyme Tests.

The belief in chronic lyme, like that of Occult Infections (Jadin, Pasteur Institute in the 1950’s) were all reasonable beliefs to explain what was observed. The key word is were. In my humble opinion, a simpler explanation is just “post infection syndrome” (with the specific infection having little consequence for the syndrome).  It is my belief, that post infection syndrome is a stable dysfunctional microbiome shift that results in similar chemicals being produced (causing the symptoms!!!) as when the infection was happening.

See How does CFS, IBS, Chronic Lyme Happen?

My wife just came in and said “But what about the family on … whose son had CFS for years, then got a Lyme diagnosis, was given antibiotics and recovered???!!!!” My answer, “That does not prove it was lyme, it only show that what ever caused “CFS/Chronic Lyme” was susceptible to the right antibiotics.” Antibiotics cause microbiome shifts — for the better or the worst, to sickness or health — with CFS, we have evidence of the shift of the microbiome and thus need to tailor antibiotics, herbal anti-bacterial, probiotics (which often produce antibiotics themselves!) to correct those shifts.

Is getting a Chronic Lyme diagnosis bad?

The answer is no – provided you can negotiate with your physician on which antibiotics to take. On my last remission, I knew what antibiotics I probably need to take — the problem is that with the concern over antibiotic-resistance, getting a physician to prescribe is almost impossible.  Where I live, naturopathic physician have the right to prescribe. I found one that worked with a Lyme MD, Marty Ross, and she (Dr.Iller, ND) was open to following a Jadin-like protocol of rotating antibiotics — however, she wanted to test for Lyme because if positive, it provided protection for her prescribing antibiotics. In short, she and I were “working the system”. I was positive for Lyme according to the labs.

The first two were minocycline and doxycycline. The improvement accelerated when I add Neem and Tulsi capsules (which impacts the overgrowth families that the prior antibiotics do not impact).

Officially, she was prescribing appropriate antibiotics for Lyme. I just spun the choices to deal with the microbiome shift reported for CFS — a win-win. Who was right? It does not really matter because what was important was the remission.

One of my classic lab tests to indicate CFS

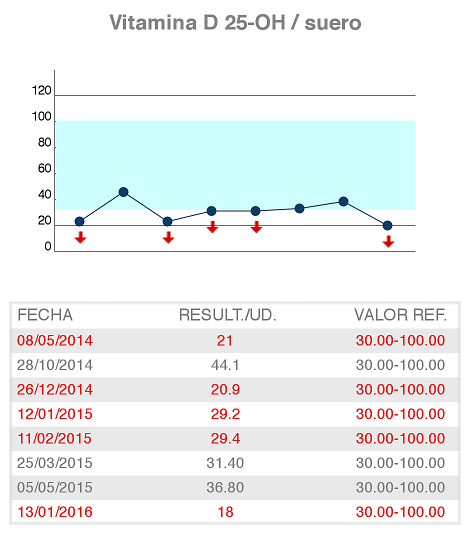
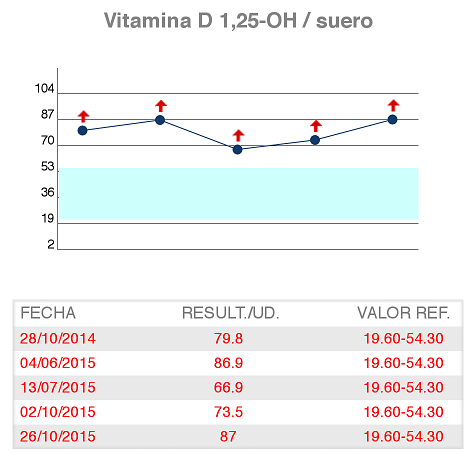
The patient in my prior post was very kind and forwarded their Vitamin D charts which are shown below. The classic fingerprint for CFS is high 1,25D  — why is unclear. I suspect that it may be due to the dysfunction microbiome but I have not found any studies exploring that. Also note, that 1,25D can go up when 25D goes down.

  • 25D is reserves — the amount of oil stored in refineries.
  • 1,25D is active  — the amount of pollution being produced by cars burning oil.
Vitamin 25D Vitamin 1-25D
25D 125D

If you do not have high 1,25D and a normal SPECT scan — get a second (or third) opinion about whether you have CFS. IMHO, there is a good chance that you have another condition! See Lazy Diagnosis, You have Chronic Fatigue Syndrome.


A Review of a Patients Labs with Suggestions

A correspondent shared much of their medical history and lab tests with me. They were discouraged with the failure to get remission. One of their key physicians is well respected by me, in other words, they have had world-class treatment already. The following is a review with suggestions to be discussed with knowledgeable medical professional.

Diagnosis: Chronic Lyme

Tick bite happened 5 years ago. They have done rotations of antibiotics that included:

Diagnosis includes coxellia ricketsia.

Analysis

There are three families of overgrowth, the first three antibiotics only effect just one of these families (see my chart). The last one appears to reduce at least two of the families that are under growths. If the symptoms are due to a microbiome shift (and not an actual lyme infection), then there is a strong need to add appropriate probiotics.

Lab Tests – Abnormalities

  • Borrelia burgdorferi Fully Antigen: 10x the detection value
  • Candida Albicans: positive
  • Magnesium: Low
  • Epstein Barr: 2x the detection value
  • C Reactive Protein: 3x the detection value
  • Cytomegalovirus Antibodies IgM: 3x the detection value
  • Vitamin D (25-OH): low, 18 ng/mL, normal range 30-100 ng/mL
  • Immunoglobulin E: 3x the detection level
  • Iron Saturation: low, 15%, normal range 25-45

Analysis

The first action should be raising Vitamin D. See these earlier posts:

The target value is 90-100 ng/mL (200-250 nmol/L). Assuming 60 kg (130 lbs), this means some 450,000 IU of vitamin D3 needs to taken for a normal healthy person. At 15,000 IU/day — it will take 30 days, At 10,000 IU/day – 45 days.

If the person is 20% heavier, than it would take 20% more days (36 days and 54 days). Note that I said normal healthy. There is evidence suggesting that CFS patients may absorb vitamin D at a rate as low as 50% of healthy individuals. This means that after 1-2 month of high dosages, vitamin D needs to be measure again to see how much increase actually happened and the dosage adjusted.

Magnesium

For Magnesium supplements, see this Magnesium and Malic Acid post.  Supplement with Magnesium Malate (if available). It is likely low because bifidobacterium is the usual bacteria that extracts it — and that is low in CFS patients.

C-Reactive Protein

This can be lowered by taking a probiotic, see my Align – Bifidobacterium infantis 35624 – a demonstrated probiotic for IBS post. “ Achieving 25(OH)D ≥ 75 nmol/l was accompanied by higher circulating LL-37, higher QoL scores and reduced CRP.” [2015]”

Alpha Lipoic Acid also reduces CRP levels (by about 19% in studies [2012]) and improves blood flow.

EBV, CMV and/or Lyme???

The labs show positive for EBV and cytomegalovirus really raise the question of a false-positive for Lyme.

  • “False-positive results of serological tests for Lyme disease have been reported in cases of recent primary infection with varicella-zoster virus [1,2], Epstein-Barr virus [3,4], and cytomegalovirus [3]. We report the first association of false-positive results of serological testing for Lyme disease with infection due to another of the herpesviruses, herpes simplex virus (HSV) type 2.” [2005]

My preferred reading is this: we know that we never get rid of a virus infection. Our immune system normally keep them in control. When the microbiome is disrupted, this control can be lost.

Supplements

The supplements reported include:

  • VSL#3,
  • Pro5 Protein Powder,
  • vitamin B12,
  • vitamin complex of group B ( jarrow formula) ,
  • zinc ,
  • iron,
  • magnesium malate ,
  • ubiquinol ,
  • omega3 ,
  • burbur ,
  • milk thistle ,
  • b6 ,
  • glutamine ,
  • alpha lipoic acid

Recommended Changes

  • Vitamin D3 – 15,000 IU/day
  • Check the dosage for magnesium malate against my earlier post, and increase the dosage if it is not at least the level reported in PubMed studies
  • Stop the VSL#3 when you finish you your current supply, use Prescript Assist instead
  • Add Align (Bifidobacterium infantis 35624)
  • Examine the list of probiotics on me-pedia and rotate to different ones when you finish a bottle or a box (hint: never buy two boxes or bottles, just one and then use it all up and rotate to the next one)
  • Start using Tulsi Tea or capsule supplements
  • Rotate capsules of the “0” and “1” herbs listed on the herb list.

D-Ribose producing bacteria

D-ribose supplementation helping CFS/FM is likely because natural production by the body is reduced. “By the body” often means by the microbiome. For example a body that produces not enough B-12, is because it is low in L. Reuteri that makes the B12.

So what bacteria makes D-Ribose? What I have been able to find via PubMed are:

See also these posts

Bacillus Subtilis

“Cultures of B. subtilis were popular worldwide before the introduction of antibiotics as an immunostimulatory agent to aid treatment of gastrointestinal and urinary tract diseases” [wikipedia]

  • “We examined two commercial B. subtilis probiotic preparations, Enterogermina and Biosubtyl. Surprisingly, physiological and genetic characterization of the bacteria contained in each of these preparations has shown that neither contains B. subtilis….. instead Bacillus species that are closely (Biosubtyl) and distantly (Enterogermina) related to B. subtilis. ” [1999]
  • “Bacillus subtilis is used to produce many antibiotics, such as difficidin, oxydifficidin, bacilli, bacillomyin B, and Bacitracin,…Bacillus subtilis is also used as a fungicide” [Probiotic.org]

Sources

While there are studies of d-ribose and CFS (positive results), there are none for bacillus subtilis. I could not find a single strain/species probiotics (excluding those cited above). The production amount of ribose is strain specific. What does contain some are:

  • Prescript Assist – effective for IBS
  • Threelac Probiotic on Amazon (60 packages for $42) – bacillus coagulans, bacillus subtilis and enterococcus faecalis  – no studies on PubMed
  • Update: Unpasturized doenjang (Korean f0od), available on Amazon.
  • Natto, a Japanese dessert food! – I do eat this, originally as a source of nattokinease, but now I have a second reason for eating it!!

001

Last, it should be mention that it is also called hay bacillus or grass bacillus because that is where it is very often found. A hundred years ago, when most of the population lived on farms, people would have gotten a rich supply of this. In today’s world, there is a greatly reduced exposure to hay or grass (and thus the bacteria).

D-Ribose revisited

I wrote about d-ribose in a post from 2012. I recommend it strongly then. Dr. Myhill writes favorably on her website – “Therefore I recommend that my CFS patients use 5 grams (1 scoop) three times a day”.

  • “Ribose was added to the existing treatment regimen of a woman with fibromyalgia, resulting in a decrease in symptoms.” [2004]
  • “D-ribose significantly reduced clinical symptoms in patients suffering from fibromyalgia and chronic fatigue syndrome.” [2006]

A reader asked me today “Is d-ribose bad for leaky gut and candida?”.  I can understand the logic leading to the question:

  • Sugar is bad for leaky gut and candida.
  • D-Ribose is a sugar.
  • Thus D-Ribose may be bad!

The fallacy is that “All sugars is bad” is an over generalization! The statement is true for normal household sugar, we need to be careful not to extend this without evidence.

See also these posts:

” These excretion patterns correlated well with the excessive oral ingestion of dairy products, artificial sweeteners and sucrose. Eliminating excessive use of these foods brought about a dramatic reduction in the incidence and severity of Candida vulvovaginitis.” [1984]

According to WebMD, “Ribose is a kind of sugar that is produced by the body. It is used as a medicine… it has also been used to improve symptoms of chronic fatigue syndrome (CFS), fibromyalgia, and coronary artery disease. ”

WikiBooks writes ” D-ribose supplements improved their conditions [CFS,FM] because it helps the patients produce more ATP in the body, because their body cannot produce a sufficient amount of ATP needed…D-ribose is a molecule that is naturally produced by the human body and is not found in food sources. However riboflavin[B2], a component of d-ribose that helps aid in the production of d-ribose, is found in a plethora of food… Convert B6 vitamin into a form the body can use.”

According to Wikipedia “In biology, D-ribose must be phosphorylated by the cell before it can be used. Ribokinase catalyzes this reaction by converting D-ribose to D-ribose 5-phosphate. Once converted, D-ribose-5-phosphate is available for the manufacturing of the amino acids tryptophan and histidine, or for use in the pentose phosphate pathway. The absorption of D-ribose is 88–100% in the small intestines (up to 200 mg/kg/h)”

Answers to the Questions

  • If almost 100% is absorbed, then it feeding candida is very suspect. I could find nothing  supporting that it increases candida.
  • Reduced levels of histidine is associated with IBD flares [2015] as is Tryptophan [2010], both would be expected to increased with d-ribose. So reduced leaky gut would be expected from adding d-ribose.

There can be side-effects, it is used by E.Coli (low in CFS patients) so a shift in the microbiome may happen — which could produce  diarrhea, stomach discomfort, nausea, headache. When you add it, add is slowly!

D-Ribose continues to be on my recommended list — especially with Mutaflor (E.Coli Nissle 1917) [2007]. It is on my frugal list of supplements – although I cite just 1 gm/day instead of the 15 grams/day of Dr. MyHill ($66/month).


Depression, Confusion, Fear – the protocol disrupters

A reader wrote today the following

“I know this will and does seem like an excuse to anyone who hasn’t suffered from CFS / Lyme and related illnesses, but I’ve been feeling so depressed and so tired and so dumb the last six plus months that following a complex protocol feels impossible. I don’t know if depression or total lack of motivation is something you’ve dealt with personally, but I would truly appreciate any advice you have. I’m hoping that if I can get some relief in that area that I will feel motivated and less defeated and more clear when trying to start and follow a protocol. “

This is not unfamiliar to people dealing with CFS patients. A lot of the problems stem from the decrease of executive function coupled with difficulty processing information. If you go to any CFS forum, you will hear dozen of opinions often with concerns about taking too much of ABC.

A classic example is concerns about taking above the recommended daily allowance (RDA). The RDA for Vitamin D is 600 IU/day but this level will never result in Vitamin D levels in the body reaching the level that has been shown to reduce symptom severity for Chronic Fatigue Syndrome and Fibromyalgia (prior post). A 2015 study found IBS quality of life improves with increase of Vitamin D. Even Doctor  Mercola states “The Institute of Medicine’s (IOM) recommended dietary allowance(RDA) for vitamin D underestimates the need by a factor of 10″ [2015] and recommend 9000 IU. Because of mal-absorption that occurs with CFS, I advocate 15,000 IU. What happens? You walk into your medical professional and tell them you are taking 9000 – 15000 IU/day and they freak out, pressuring you to reduce it to just 600 IU — because that is what is in the official literature.

Most CFS patients ends up having to make their own decisions on what to take and dosages — and with limited cognitive abilities, that is a challenge.

Dealing with Depression

This is a good point to start a list of daily supplements.

  • ” evidence of decreased depression risk among women with higher intakes of vitamin B6 from food, which was dependent on total energy intake, and among men with higher intakes of B12 from food” [2015]
  • “vitamin B consumption and serum vitamin B12 and folic acid levels were low …among patients with depression.” [2015]
  • ” men with deficient vitamin D status were more likely to have current major depressive disorder… Associations among women were not significant” [2015]

So three vitamins should be taken daily

  • Vitamin D3: 9000-15000 IU/day
  • Folate (B9) – 6,000-13,000 mcg – See this post for studies.
    • “. A remarkable 81% of CFS patients experienced subjective improvement of their symptoms after treatment with folinic acid” [2006] [Full Text] [Amazon] 800 – 1600 mcg /day – The folinic acid form is biologically active, not plain folate.
  • B12 – 1000 mcg/ 1 mg seems to be the effective ongoing dosage, see this post
  • B6 supplementation have been reported to be problematic, I need to do more research

To Avoid: Lactobacillus Acidophilus, a recent study found that higher levels were associated with depression

To Take: See CFS Depression, Diet and the Microbiome

Confusion

Every decision that you must deal with, adds confusion. I have seen patients selecting pills to be exhausting.

One approach that I have done with people that are irregular in taking supplements is to prepare 7 zip-lock bags labelled (Monday, Tuesday, … Sunday). Sorting and selecting pills only need to be done once a week.

Combining these bags with a marker pen that writes the number of capsules from each bottle (as shown below), eliminates the decisions to be made. For many supplements (except anti-infection ones), keep taking the number specified until the bottle is empty.  Many CFSer end up with 1/2 or 3/4 filled bottle of supplements that they stop taking (which does not help a tight budget!).  When the bottle is done, consider a different one OR refill OR BOTH!

IMG_20160223_193646

Fear

Fear is a harder item to deal with.  One resolution of not having a cure from the MDs is to simply wait until a cure is found.  Will a specific treatment make me worst?  An adverse reaction associated to something reported on a forum can result in significant fear about taking something — even when studies have found strong positive effects.

For me, when I was in relapse with CFS, I kept to items with demonstrated positive effects according to PubMed, if some one (even a MD) suggestions something contrary I asked for a pubmed article supporting their belief. If they cannot provide one, then I ignore them — End of influence.  Information from forums, while emotionally nice and supportive, are often coming from people with cognitive impairment, poor memory etc etc etc. The information actually comes with significant costs to a CFS patient — a lot of noise that can be very difficult to sort thru.

Where do you go from here?

Three vitamins should decrease depression significantly as well as improve symptoms. If you have been eating yogurt or probiotics high in L. acidophilus, you may wish to stop.

You want to simplify pill taking — do 7 days of pills and do it by only figuring out the dosages ONCE instead of every day.