Un resumen de mis experiencias y modelo de ME / CFS

“He estado en el mundo ME / CFS por unos 20 años”. Los síntomas cada vez fueron diferentes, pero con algunas coincidencias. Las pruebas de laboratorio y la exploración cerebral confirmaron que cada vez que se trataba de EM / SFC.

Mi formación: soy un científico con un gran énfasis en modelar sistemas e interacciones (con varios cursos de nivel de doctorado completados). Comencé con la creencia popular del día, hace unos 20 años, y encontré tratamientos que funcionaron para mí (pero el razonamiento de que el tratamiento funcionó fue ligeramente incorrecto, en mi humilde opinión). Esos eran el Protocolo de Hemex y el Protocolo de Jadin.

Los mismos tratamientos no funcionaron para otros. Soy curioso por naturaleza y probé docenas de modelos para explicar los síntomas y el éxito / fracaso del tratamiento. Estaba en un programa para niños muy talentosos y comencé a leer revistas médicas a los 14. También tengo una maestría en estadística y sé cómo las revistas pueden hacer un giro de sus resultados. En otras palabras, puedo clasificar el valor actual para el tratamiento de cada estudio.

Hace unos ocho años, tuve que recaer debido al estrés laboral (trabajando para Amazon en Data Science). Al releer toda la literatura / artículos publicados de ME / CFS, me encontré con el estudio de Australia de 1999 que informaba los cambios en el microbioma.

Esto hizo que intentara construir un modelo para que el EM / SFC sea un trastorno microbiológico. Con un modelo, obtienes la capacidad de predecir y, por lo tanto, probar si el modelo parece correcto. Mirando lo que funcionó para mí, vi que lo que hice alteraría mi microbioma. A lo largo de los años, cada vez más estudios confirmaron que el modelo parece ser correcto.

Es una explicación simple, y explica que diferentes personas tengan diferentes síntomas (ya que es probable que los síntomas estén agrupando bacterias específicas). También da cuenta de diferentes reacciones a diferentes cosas. Tiene un alto contenido de bacterias ‘sensibles al gluten’, es sensible al gluten, tiene un alto contenido de bacterias productoras de histamina, tiene problemas de histamina.

Para el brote en el que estoy actualmente, he pasado de estar enfermo durante toda la semana con una lista masiva de síntomas a la planificación para trabajar 6 horas al día la próxima semana con solo unos pocos síntomas restantes. Los síntomas restantes incluyen que mi cutis se vuelva gris si voy más allá de los límites evolutivos (por ejemplo, visitar a un amigo demasiado tiempo en una cafetería). Esto es durante un período de cinco semanas. No tengo antibióticos ni medicamentos recetados: solo obtengo los resultados de mi microbioma y los probióticos (Bacillus Clausii, SymbioFlor-2 principalmente) y muchas nueces (tomar un puñado de Almendras para el desayuno es mi norma actual).

Acabo de sentir en una nueva muestra de microbioma y probablemente tendré que volver a modificar las cosas cuando lleguen los resultados.

Sí, muchas cosas por ahí son correctas. Cosas como los cambios de TH1 / TH2. Como científico, mi formación es clara:

El modelo más simple que explica la mayoría de las observaciones, cuanto más preferido es.
Un modelo debe tener la capacidad de predecir, generar experimentos para probar que se prueben. El éxito repetido en experimentos construye confianza.
Ningún otro modelo viene a explicar los síntomas y las respuestas con ME / CFS. El modelo también proporciona una explicación clara y aceptada para un cambio TH1 / TH2.

Para mí, no diré que otros modelos están equivocados, son posibles. Cuando se trata de la probabilidad de ser correcta, las probabilidades son similares a las de un boleto de lotería.
Icelandic Disease, Polio and Up-regulation of Immune System.

Recently I saw on Facebook:

“Reading a book about CFS and although I knew there was a big outbreak of CFS in a region of Iceland in the 1940’s (over 1000 cases, mostly high school students), I didn’t know that 7 years later the same region of Iceland had a serious Polio outbreak and for some reason all of those who had gotten CFS were immune to the Polio virus. This led some researchers to believe that there is a virus that causes at least some cases of CFS and it may be closely related to Polio.”

I recall reading this in Osler’s Web: Inside the Labyrinth of the Chronic Fatigue Syndrome Epidemic(1996) back in 2000. I also read of the appearance of the immune system being up-regulated because CFS patient rarely catch other illness. Iceland or Akureyri Disease and polio is described in this study.

The light went on today that the microbiota hypothesis would explain both of these observations perfectly.

If we assume that most infections reprogram the microbiota by sending deceptive chemical signals to produce the chemicals it needs, or to surpress the chemicals it does not want then things become obvious.

If another infection comes along, it’s attempt to reprogram will likely fail. Without the chemicals to supply it’s reproduction the infection fails to get established.

This actually leads to the stable microbiota dysfunction being of evolutionary advantage. Having 2-4% of the population in this state means that if a nasty nasty deadly infection hits a population, this group will survive while all around them the healthy microbiota folks are being reprogrammed to eventually kill the person.


Memory Issues and Gut Bacteria

During my last CFS episode I had a SPECT scan done. The results matched that reported on PubMed for chronic lyme and for chronic fatigue syndrome. I was having severe memory issues, especially short term and recent events. The radiologist read the SPECT as indicative of Alzheimer’s Disease. The areas of the brain impacted were the same area seen with Alzheimer. With recovery, memory issues reduced every month. I suspect it could easily be 2 years before I hit the 99.9999% of my prior level. I suspect that my SPECT will be near normal if done again. Many people will not notice the memory issues remaining, but I frequently (daily) notice minor memory failures for example inability to recall a word or tie a name to a face.

Since the recovery of memory was a result of actively altering gut bacteria, it suggests that old age dementia and Alzheimer’s Disease may have a very significant cause being gut bacteria.

Looking at pub med, there are just two studies that have looked at AD and the microbiota, both published in 2013:

Age-Related Memory Issues

There have been several studies on how gut bacteria changes with age:

  • Role of the gut microbiota in age-related chronic inflammation. (2012) “A growing body of literature implicates age-related perturbations in the gut microbial ecology as contributing to a global inflammatory state in the elderly.”
  • Enteric pathogens through life stages. (2012) – Full Text Free “Recent gut microbial surveys have indicated dramatic shifts in gut microbial population structure from infants to young adults to the elders.”
  • Aging of the human metaorganism: the microbial counterpart. (2012) – Full Text Free (and an excellent article that details results from specific species of probiotics!)
    “The total diversity of a healthy adult gut ecosystem is generally reported to be around 1,000–1,200 species.. of which 75–82% is estimated to remain uncultured.” This means that we likely have no idea of what 75% of the bacteria produce or interacts..

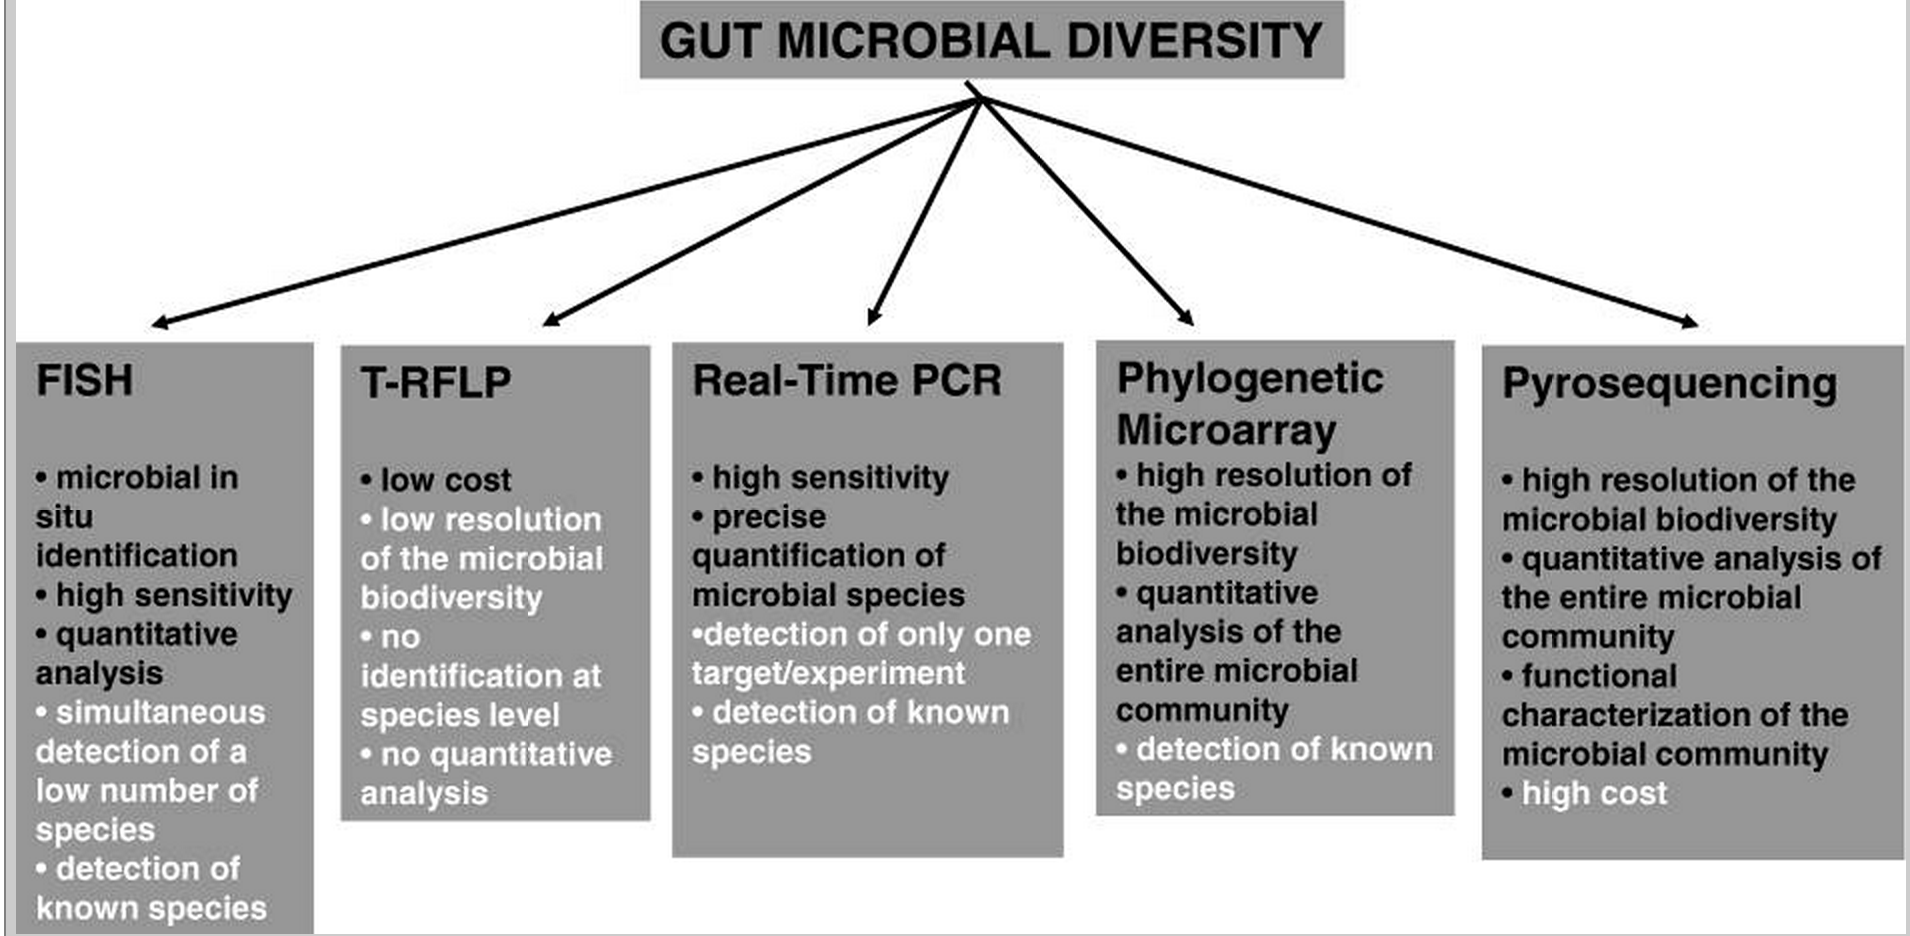
The question of testing often arises, the above article summarizes the current state of testing:

The prosequencing is what is needed. We have more unknowns than knowns…

I am hoping that there will be studies of Prescript Assist and Mutaflor on neurodegenerative diseases — I suspect that the results will be very interesting.


Recent news stories dealing with Gut Bacteria and impact on entire life…

Should CFS Patients use Lactobacillus Acidophilus? -Probably not

The studies behind this opinion may flies in the face of many physicians opinions (ND and MD) . The reason is the nature of the gut bacteria found in their guts. For many other conditions, Lactobacillus Acidophilus has proven health benefits. This is not the case with CFS.  I have read conference reports where CFS specialist have politely stated that they “have not seen any benefit from [normal] probiotics” — I would go further and suggest that it may be harmful to the CFS patient’s health.

The first study is Faecal Microbial Growth Inhibition in Chronic Fatigue/Pain Patients, presented at the AHMF conference in 1998 (The Manly Conference). The population of  E.Coli species was about 50% of normal in a sample of 27 patients. Richard Schloeffel reported finding extremely low E.Coli population in Two Case Studies of Successful Treatment of CFS/M.E. at the 2001 conference. Both Dr. Sarah Myhill (Wales, UK) and Dr. Kenny DeMeileir (Belgium) prescribes E.Coli probiotics for their patients.

This suggests that you want to encourage (healthy) E.Coli growth and avoid things that kill E.Coli.

Unfortunately Lactobacillus Acidophilus kills E.Coli as the following studies state:

and many more…  Lactobacillus Acidophilus (and some other species) are not the way to restore a CFS patient’s gut — if anything, it will keep it with low E.Coli populations.