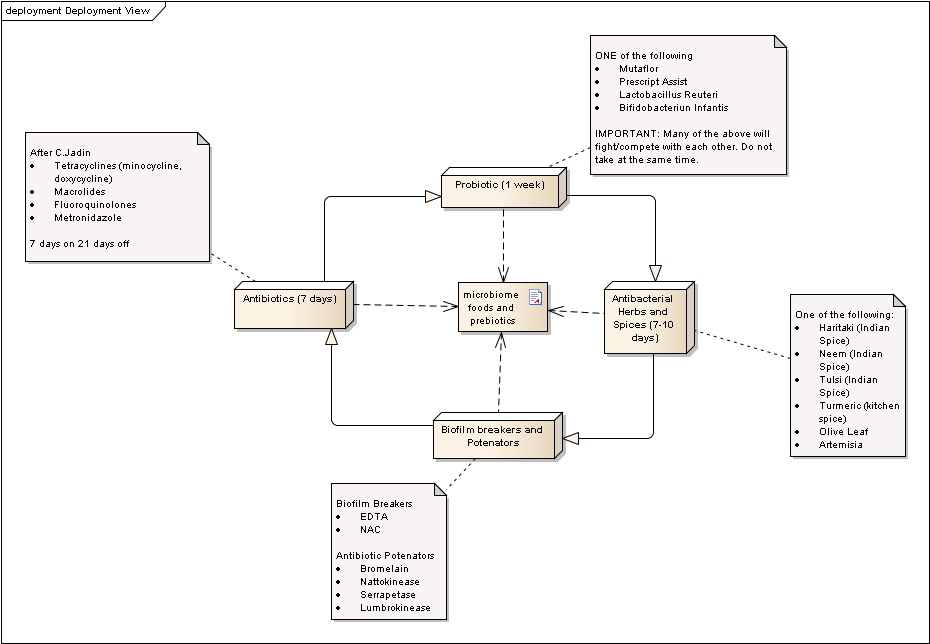
Treatment Model: The 4 week cycle


I decided that a graphic of the method that I have found to be effective may help. Every week there is a change:

  • Adding good probiotics one week
  • Killing bad bacteria the next week
  • Exposing bad bacteria the next week
  • Killing bad bacteria the next week.

If you want more good probiotics cycles, then just add them after doing something else. If you do not wish to do antibiotics, then it becomes a three week cycle instead.

Treatment Cycle

Bifidobacteriun Infantis – another interesting probiotic

Health Rising did a recent post on Bifidobacteriun infantis 35624. There are some 27 hits on pubmed on this probiotics, not as many as for Mutaflor, but respectable. The latest study is available in full text and found that inflammation of CFS patients decreased significantly. Another study found the amelioration of symptoms of irritable bowel syndrome (but required constant use).  Since IBS and CFS are co-morbid to a large extent, the two studies confirm each other’s results.

The need to constantly take it, makes the manufacturer, The Procter & Gamble Company, probably very happy (and partially accounts for the studies occurring).

This specific species is available on amazon.com, the price clearly shows that P&G is seeking a premium market.

Since the full text is available for free, it may be worthwhile to at least read them for information on the experience of taking an effective probiotic.

Lactobacillus Reuteri and recommendations on how to take it

Update: 2018 Summary on L Reuteri.

Lactobacillus Reuteri is near the top of my list of probiotics. The reason is simple, in almost all mammals it is the species that is usually most seen in healthy individuals. Often studies reported something like 55% of the Lactobacillus species are Reuteri. It is NOT in most probiotics. L.Reuteri is by far the Lactobacillus that is most likely to persist in the gut, most Lactobacillus are literally flow-thru, they have an impact, (in fact, one antibiotic (not used much today) is extracted from Lactobacillus Acidopholus), but do not establish a colony. It produces reuterin and cobalamin (B12), which no other Lactobacillus does.

My own practice is to buy as many different strains of L.Reuteri that I can find. For maintenance, I do a week of it every 2-3 months. It should be taken before meals and with some fat, see this post for details.

For a more technical description of L.Reuteri, see

Glutathione

Glutathione is one of L.Reuteri essential foods (http://www.ncbi.nlm.nih.gov/pubmed/21585317 ) so make sure that you supplement with it (I would suggest taking that 1 hr before the L.Reuteri) . This feeding of L. Reuteri may be one reason that it has positive effects on CFS patients (although the why of taking it comes from a different model).

The reason that some people may be non-responders to Gluthathione could be as simple as having no L.Reuteri left to feed!

Bottom line:  L Reuteri and Glutathione should be taken together – taking one without the other may result in little or no effect.

Finally! Someone verified the 1999 Studies – Thank you Kenny!

I have been running my Microbiome Hypothesis after a study from 1999 which no one had attempted to replicate for 14 years. Finally in the Anaerobe journal on 18 June 2013, High-throughput 16S rRNA gene sequencing reveals alterations of intestinal microbiota in myalgic encephalomyelitis/chronic fatigue syndrome patients confirms that there is a distinct alteration!

Many thanks to


Available online 18 June 2013

In Press, Corrected Proof — Note to users

Cover image
Clinical microbiology

High-throughput 16S rRNA gene sequencing reveals alterations of intestinal microbiota in myalgic encephalomyelitis/chronic fatigue syndrome patients ☆

Open Access Article
  • a R.E.D Laboratories NV, Z-1 Researchpark 100, 1731 Zellik, Belgium
  • b Biostatistics and Medical Informatics Department, Vrije Universiteit Brussel, Laarbeeklaan 103, 1090 Brussels, Belgium
  • c DNAVision SA, Av. Georges Lemaitre 25, 6041 Gosselies, Belgium
  • d Department of Human Physiology, Vrije Universiteit Brussel, Pleinlaan 2, 1051 Brussels, Belgium

Highlights

•

We looked for alterations of gut microbiota in chronic fatigue syndrome patients.

•

Patients and controls from two geographical origins were included in the study.

•

Gut flora composition differed between people from different geographical origins.

•

Significant alterations of gut microbiota composition were observed in patients.


Abstract

Human intestinal microbiota plays an important role in the maintenance of host health by providing energy, nutrients, and immunological protection. Intestinal dysfunction is a frequent complaint in myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) patients, and previous reports suggest that dysbiosis, i.e. the overgrowth of abnormal populations of bacteria in the gut, is linked to the pathogenesis of the disease.

We used high-throughput 16S rRNA gene sequencing to investigate the presence of specific alterations in the gut microbiota of ME/CFS patients from Belgium and Norway. 43 ME/CFS patients and 36 healthy controls were included in the study. Bacterial DNA was extracted from stool samples, PCR amplification was performed on 16S rRNA gene regions, and PCR amplicons were sequenced using Roche FLX 454 sequencer.

The composition of the gut microbiota was found to differ between Belgian controls and Norwegian controls: Norwegians showed higher percentages of specific Firmicutes populations (Roseburia, Holdemania) and lower proportions of most Bacteroidetes genera. A highly significant separation could be achieved between Norwegian controls and Norwegian patients: patients presented increased proportions of Lactonifactor andAlistipes, as well as a decrease in several Firmicutes populations. In Belgian subjects the patient/control separation was less pronounced, however some abnormalities observed in Norwegian patients were also found in Belgian patients.

These results show that intestinal microbiota is altered in ME/CFS. High-throughput sequencing is a useful tool to diagnose dysbiosis in patients and could help designing treatments based on gut microbiota modulation (antibiotics, pre and probiotics supplementation).

<Nag>I hate to say it, but I am already attempting by this blog and cortjohnson.org blog trying to do just that based on my own experience of going into remission by doing exactly that!</Nag>

The methods need to be improved, bigger sample populations and using tests that identify the specific strains — but it is a start!

We have a Ken and a Kenny on the same page!


How vaccines can cause Chronic Fatigue Syndrome – a Model

I saw this in the news today:
The vaccine known as hepatitis B has been ruled by a United States Court of Federal Claims that “a dose of the hepatitis B vaccination caused [a patient] to develop chronic fatigue syndrome.”  Article

This type of claim has been asserted many times and view skeptically by many (including me, once upon a time).

How do vaccine work? Usually they provoke a minor version of the disease or a close relative (for example, one of the first vaccines used cow-pox to protect from smallpox).  This is now it happens… whether you have a mild form or a severe form, the infection causes some alteration of the microbiota. If the microbiota returns to its prior state, there is no problems. If the microbiota does not return but stays in it’s altered state then we slide into Chronic Fatigue Syndrome.  It is that simple!!!

Should you avoid vaccines? In general, vaccines are good for the general population and result in a significant benefit from having less deaths and illnesses. I went to school and later taught with someone that had Polio as a child and apparently recovered fully. She later was confined to a wheelchair (a too common occurrence with those that recovered from polio as a child).  Would I tell anyone not to get a Polio shot?  Absolutely not, unless there is autoimmune in the person’s  blood relatives. If there are, then I would say avoid it — the risks are significantly higher for problems.

This is the conclusion of a 2005 study:
In genetically susceptible individuals or together with some other triggers such combination might confer the risk of developing a continuous autoimmune response in an individual. Anti-phospholipid antibodies following vaccination with recombinant hepatitis B vaccine.

NOTE:  a variation of anti-phospholipid syndrome (Hughes Syndrome) is what Dave Berg (Hemex) described the coagulation issues he saw in CFS patients.

One recent study is interesting:

Transiently or persistently increased levels of autoantibodies or appearance of new autoantibodies was demonstrated in up to 15% of apparently healthy adults after the influenza vaccination. http://www.ncbi.nlm.nih.gov/pubmed/18700173

Microbiota tend to be inherited in families, thus the presence of autoimmune in blood relatives implies (but does not prove) a greater risk of the microbiota not returning to normal.

So, do I believe that vaccine can cause CFS — yes, because there is both a model to explain how and published studies describing the the appropriate changes do occur.