Blastocystis hominis infections? Ignore or act?

A reader wrote me because of progress with medical professionals have not happen and there have been significant apparent side-effects from

“on the that meeting with the doctor I discussed my parasitic infection with blastocystis hominis, and the s.boulardii treatment so he prescribed to me OMNIFLORAN (  (Lactobacillus gasseri and Bifidobacterium longum) & Perenterol Forte.  (Saccharomyces cerevisiae)

I started taking both but due to constipation that became more severe I decided to stop & wait 1 week then start with the yeast first and then introduce the probiotic.
After around 10 days +- of taking it a very strange thing happened to me (was almost 3 weeks ago) , while doing my workout which I regularly do, in one of the trainings that I didn’t do a warm up & started squatting with a heavier than usual weights I felt a pinching pain in the knees, continued a bit and then removed the weights and went on with the workout.
2-3 days later I start feeling muscle and joint paint in my entire body but especially my legs. I’m used to getting sore muscles but they recover and are not that bad, this time it continued and I couldn’t sleep well & had to put my legs on a pillow, couldn’t exercise as I used to be very active and so on.
I went to massages which relieved it a bit but still I had pain around joints (like pinching) when I bend or do sharp movements, and stiffness in my ankles that was so awful. I also felt weak, tired & super exhausted.
To make it a bit shorter, after 2 weeks of massage with physiotherapists, ultrasound and some electric differentiation treatment with high doses of vitamin C,E & magnesium I started to feel better. In the 3rd week now I started to move a bit and do some yoga and treadmill walking with some exercises for improving hip rotation and strengthening the knees but it is still a bit difficult.”

What does the literature report?

I cannot advise what a reader should do, such must come from medical professionals. What I can do is simple report what is in the literature (with links to the literature) for educational purposes.

  • “Blastocystis hominis, previously considered a harmless yeast, is now classified as a protozoan inhabiting the human intestinal tract. The pathogenicity of B. hominis remains controversial and is currently the subject of extensive debate. As a result of the uncertainty surrounding the pathogenic role of B. hominis, large-scale treatment trials of B. hominis infection have so far been lacking. In spite of this, several drugs have been reported to be active against the parasite.” [2003]
  • “Because of this vast diversity, it has been suggested that the human parasite should no longer be referred to as Blastocystis hominis but instead should be called Blastocystis spp. or Blastocystis spp. subtype n (where n is the subtype number according to the Stensvold classification)” [2012]
    • “There has been debate in the literature concerning the question of the pathogenicity of Blastocystis. Some studies suggest an association between the parasite and disease, but others do not [3, 18, 21]. “
    • “A causal relationship has never been established for Blastocystis and diarrhea, and no reliable animal model exists, so Koch’s postulates have not been demonstrated for this organism. “
    • “in some studies, Blastocystis was detected more frequently in patients with IBS than in a control group [27, 32, 35], whereas in other studies there was no association [18, 44]. “
    • “Metronidazole is considered first-line treatment, but the success of eradicating Blastocystis with this drug has been reported to be anywhere from 0% to 100% [53]. “
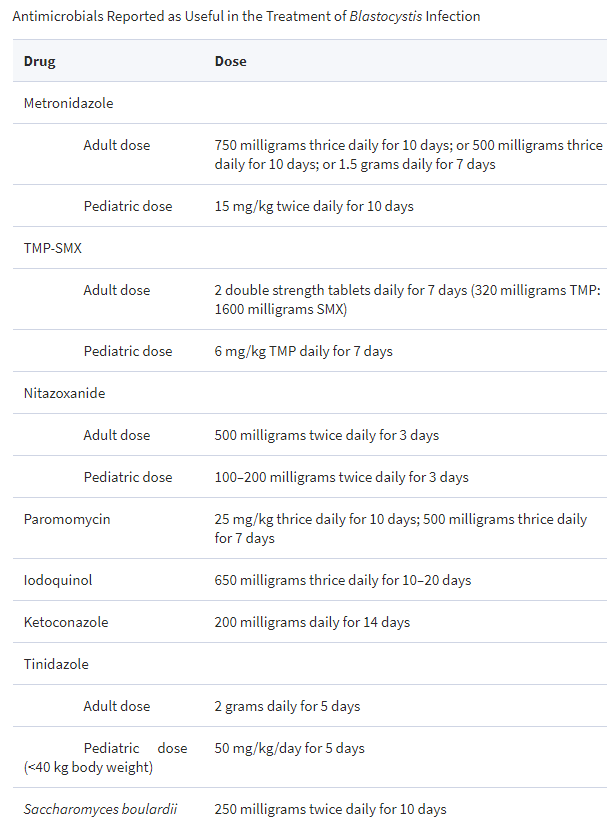
    • blast
  • “Parasite infection by B. hominis is one of the most common diseases in our tropical medicine unit. Most patients are asymptomatic, or their symptoms can be attributed to other parasite infections. In those cases in which symptoms persist without being able to attribute them to other causes, a specific treatment is recommended.” [2018] i.e. a vacation to a tropical area, risks infection.
    • “Parasitic stool testing in newly arrived refugees in Calgary, Alta.” [2017]. 30-40% has parasites. Since refugees often end up in food service, there is a risk that eating out risks infection.
  • “In Poland, the subtypes ST1, ST2, ST3, ST4, ST6 and ST7 have been reported in humans so far. ” [2017]  i.e. there are multiple types
  • Low efficacy of metronidazole in the eradication of Blastocystis hominis in symptomatic patients: Case series and systematic literature review. [2017]
  • Modulating the Gut Micro-Environment in the Treatment of Intestinal Parasites. [2016]
    • “In fact, B. hominis is probably the most common protozoan detected in human faecal samples worldwide. Infection occurs in both immune-competent and immune-compromised individuals. Reported prevalence ranges from 2%–50% with the highest rates reported for developing countries with poor environmental hygiene. Infection appears to be more common in adults than in children “
    • “An additional clinical study that administered S. boulardii or metronidazole showed potential beneficial effects in B. hominis infection relative to a reduction of symptoms and presence of parasites [19].”
  • Clinical efficacy of Saccharomyces boulardii or metronidazole in symptomatic children with Blastocystis hominis infection.[2011] – 93+% cure rate in children with either reported. S. boulardii (250 mg twice a day,

Mayo Clinic

“If you have blastocystis without signs or symptoms, then you don’t need treatment. Mild signs and symptoms may improve on their own within a few days.

Potential medications for treating blastocystis infection include:

  • Antibiotics, such as metronidazole (Flagyl) or tinidazole (Tindamax)
  • Combination medications, such as sulfamethoxazole and trimethoprim (Bactrim, Septra, others)
  • Antiprotozoal medications, such as paromomycin, or nitazoxanide (Alinia)

However, keep in mind that response to medication for blastocystis infection varies greatly from person to person. And, because the symptoms you’re having might be unrelated to blastocystis, it’s also possible that any improvement may be due to the medication’s effect on another organism.”

Bottom Line

There appears to be no firm evidence that blastocystis infections need treatment. It appears to be an opportunistic infection that simply grows as a result of other issues. Those other issues are what should be treated.

The reader took Saccharomyces cerevisiae (NOT Saccharomyces boulardii) for 10 days. I could find no literature that this probiotic is effective for blastocystis infections.

Saccharomyces cerevisiae  impacts the microbiome also. I have nothing in my database on the impact of this on the microbiome. This reader also included her KyberKompact Pro report. The report showed the typical profile commonly seen:

  • Low Lactobacillus
  • Low Bifidobacterium
  • Low Escherichia Coli
  • Low Enterococcus spp.
  • Low Faecalibacterium prausnitzii
  • Low Akkermansia muciniphila

For S. Cerevisiae, I found:

  • “Administration of S. cerevisiae RC016 caused the decline of a logarithmic unit for Enterobacteriaceae counts compared to the control.” [2016] – making the low Enterococcus worst.
  • “SCB consumption positively influenced the establishment of the Porphyromonadaceae and Ruminococcaceae bacterial families in the colon. ” [2015]

Best suggestion moving forward:

  • Get a uBiome done (simply because it gives more information!)
  • Assume Enterococcus reduction is contributing to the symptoms.

See Enterococcus [genus] undergrowth for changes in diet that may help. Suggestions are:

  • Bioflorin Enterococcus faecium SF 68
  • Reservatrol (aka. Red Wine polyphenol)
  • Sesame cake/Meal
  • Buckwheat
  • Navy and broad beans.

This is an education post to facilitate discussing this approach with your medical professionals. It is not medical advice for the treatment of any medical condition. Always consult with your medical professional before doing any  changes of diet, supplements or activity. Some items cites may interfere with prescription medicines.
 

Depression Recap and possible pure diet intervention

My earlier posts were done before I had build up an analysis application for modifying the microbiome.

Depression often runs in families. The earlier naive assumption is that it was inherited by DNA. Today we know that both DNA and microbiomes are inherited. The microbiome is much easier to modified than DNA. This title says it well:
“The relationship between dietary quality, serum brain-derived neurotrophic factor (BDNF) level, and the Val66met polymorphism in predicting depression.[2017]

  • “Higher dietary quality was associated with both decreased depression incidence and severity in this cross-sectional analysis. “

DNA Aspect

There is some associations that have been found, but no simple smoking gun at present, a few recent papers

Diet and Depression

Direct Studies on Depression

  • ” Low intake of riboflavin[Vitamin B2] was associated with an increased risk of depression in women but not in men.” [2016]
  • “An “omnivore” like diet high in amino acids, cobalamin [Vitamin B12], zinc, phosphorus, saturated fat, cholesterol and pantothenic acid[Vitamin B5] is associated with reduced psychological disorders. ” [2018]
  • Vitamin B-6 and depressive symptomatology, over time, in older Latino adults.[2018]
    “Our data suggest that identification and treatment of vitamin B-6 deficiency may be a useful preventive approach in this population.”
  • Saffron (powder or tea)
    • ” The administration of a standardised saffron extract (affron®) for 8 weeks improved anxiety and depressive symptoms in youth with mild-to-moderate symptoms, at least from the perspective of the adolescent. However, these beneficial effects were inconsistently corroborated by parents.” [2018]
    • ” In fact, saffron with its active ingredients (Crusin and Saffranal) by serotonin and dopamine secretion in the brain, help in reducing depression among recovered consumers of methamphetamine living with HIV/AIDS.” [2018]
    • ” Saffron has beneficial effects on depression and homocysteine level in patients with major depression.” [2018]

Microbiome

Some of the newer articles:

  • “Compared with their healthy counterparts, increased Actinobacteria and decreased Bacteroidetes levels were found in female and male MDD patients, respectively.” [2018]
  • “As a result, 279 significantly differentiated bacterial proteins (P<0.05) were detected and used for further bioinformatic analysis. According to phylogenetic analysis, statistically significant differences were observed for four phyla: Bacteroidetes, Proteobacteria, Firmicutes, Actinobacteria (P<0.05, for each). Abundances of 16 bacterial families were significantly different between the MDD and healthy controls (P<0.05). ” [2018]
  • “10 clinical trials with a total of 1349 patients were reviewed, comparing the use of probiotics to placebo controls. There was no significant difference in mood between the treatment and placebo group post-intervention”  [for depressive symptoms] [2018] – These studies are likely for “standard” probiotics (Lactobacillus, etc).
  • ” (R)-ketamine, but not lanicemine, significantly attenuated the altered levels of Bacteroidales, Clostridiales and Ruminococcaceae in the susceptible mice after chronic social defeat stress (CSDS).” [2017]

Diet Only Interventions Possibilities:

  • B Vitamins:
    • B2
    • B5
    • B6
    • B12
  • Amino acid supplementation
  • Zinc,
  • Phosphorus,
  • Saturated fat,

From the microbiome site, we have the following recommendations as generic results.

  • Barley
  • Walnuts
  • Cranberries
  • Fish Oil
  • Pomegranates
  • Biotin (Vitamin B7)
  • Peas
  • Baby aspirin

Do not go:

  • Gluten-free
  • Avoid high sugar content

This is an education post to facilitate discussing this approach with your medical professionals. It is not medical advice for the treatment of any medical condition. Always consult with your medical professional before doing any  changes of diet, supplements or activity. Some items cites may interfere with prescription medicines.


Are probiotics 100% safe – No, Just 99.99% safe

A reader messaged me about the safety of soil based organisms probiotics. I have touched on this a year ago in another post, there have been more studies since then. For hundreds of thousands of years, soil based organism was a part of our diet. I recall reading that the human gut bacteria has strong similarity to that seen around root vegetables. This is not surprising, pulling roots out of the ground (without washing!!!) was likely common for most of these thousands of years…

“But I read about someone getting sick from SBO!”

Well, there is similar risk from eating “safe” lactobacillus probiotics, cheese, yogurt, etc. Even deaths have been reported: “Lactobacillus-Cause of Death ” [2010]

” Lactobacillus has been used as a probiotic bacteria to treat diarrhea and is also present in dairy foods. It is hence commonly used. Lactobacillus endocarditis, an exceedingly unusual disorder, is accompanied by high mortality and poor response to treatment. ” – OUCH!

  • “In recent years, infections caused by Lactobacillus and Bifidobacterium made up 0.05% to 0.4% of cases of endocarditis and bacteremia. In most cases, the infections were caused by endogenous microflora of the host or bacterial strains colonizing the host’s oral cavity. According to a review of cases of infections caused by bacteria of the genus Lactobacillus from 2005 (collected by J.P. Cannot’a), 1.7% of infections have been linked directly with intensive dairy probiotic consumption by patients. ” [Lactic acid bacteria and health: are probiotics safe for human?]. [2014]

Some more citations…’ bacteremia is a bad bacteria infection, endocarditis is a bacteria infection of the heart. It has been only in the last few years

Bottom Line

Probiotics are generally safe. No probiotic is 100% safe. To me, soil based bacteria are likely more beneficial then lactobacillus because they went along with our ancestor’s diet long before we started domestication of milk producing animals. There may be considerable basis to the hygiene hypothesis which would result from our modern pathological obsession with sterilization of food in the belief that all bacteria are bad.


Attention-deficit syndrome and microbiome

Cognitive impairment is common in CF[2017]. A reader asked about ADHD, the hyperactivity of Attention–deficit/hyperactivity disorder is not typically reported, but the attention disorder is. There is not much published yet, but a few items were interesting:

“Attention-deficit/hyperactivity disorder (ADHD) is a neurodevelopmental disorder associated with abnormalities in dopamine neurotransmission” [2017]

  • “In a cross-sectional observational study, 123 previously confirmed FMS patients were screened for adult ADHD using the World Health Organization Adult ADHD Self Report scale v1.1. … Of the 123 participants, 44.72% (N = 55) screened positive for adult ADHD. [2017]
  • “CFS patients were assessed for childhood and adult ADHD by clinical interview and ADHD-specific scales. Psychopathological comorbidities were evaluated by clinical examination and questionnaires. Forty-seven of 158 CSF patients (29.7%) were diagnosed of childhood ADHD and in 33 (20.9%), the condition persisted into adulthood. CFS patients with adult ADHD had an earlier CSF onset, more severe anxiety and depression symptoms, and a higher risk of suicide than CFS patients without ADHD. ” [2012]
  • “Although the cause of primary Restless Leg Syndrome(RLS) is still unknown, there is a strong connection between central metabolism of iron as well as dopamine levels and RLS manifestation. ” [2011]

Bacteria Shifts

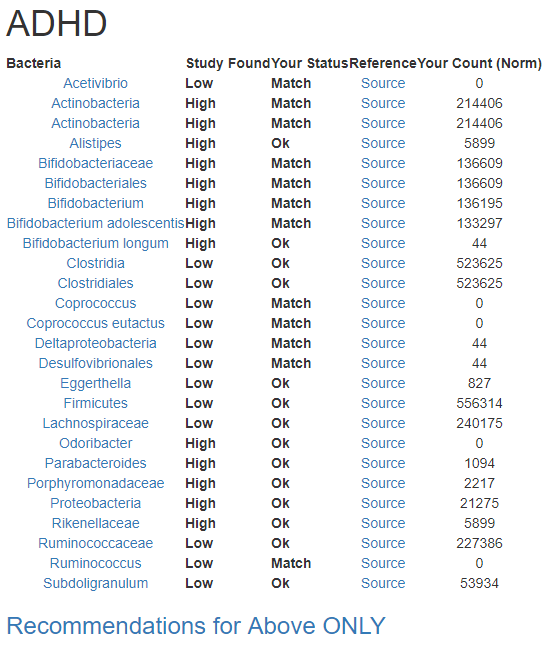
A recent article  [2017] reported the following shifts

  • Increased Bifidobacterium
  • Increase of Actinobacteria
  • Increased Bifidobacteriales
  • Increased Bifidobacteriaceae
  • Increased Bifidobacterium Longum
  • Increased Bifidobacterium adolescentis
  • Increased Bifidobacterium Pseuodocatenulatum
  • Decreased Firmicutes
  • Decreased Clostridia
  • Decreased Clostridiales
  • Decreased Ruminococcaceae
  • Decreased Subdoliggranulum
  • Decreased Ruminococcus
  • Decreased Acetivibrio
  • Decreased Lachnospiraceae
  • Decreased Coprococcus
  • Decreased Coprococcus eutactus
  • Decreased Eggerthella
  • Decreased Desulfovibrionales
  • Decreased Deltaproteobacteria
  • Increased Proteobacteria
  • Increased Porphyromonadaceae
  • Increased Odoribacter
  • Increased Parabacteroides
  • Increased Rikenellaceae
  • Increased Alistipes

uBiome Analysis Page

If you have uBiome, after uploading/logging in, go to:
http://microbiomeprescription.com/condition/condition?code=3 

And you can see how closely you match the profile.

ADHD.PNG

As always with these conditions, recommendations are available to address the bacteria shifts associated with the conditions.

Bottom Line

The available study was done on Attention–deficit AND  hyperactivity combined. We do not know which bacteria is associated with with. I would challenge the statisticians / AI / machine learning types to work from the above bacteria and the reported symptoms to try isolating those that are attention-deficit related.

This is an education post to facilitate discussing this approach with your medical professionals. It is not medical advice for the treatment of any medical condition. Always consult with your medical professional before doing any  changes of diet, supplements or activity. Some items cites may interfere with prescription medicines.


Ran into some issues using…

Ran into some issues using “ubiome” in the website name address.

Site is now:
http://microbiomeprescription.com/

I had to roll back to an older version of the site — because I was in the midst of an enhancement.

No data has been lost.