uBiome with low diversity and significant recovery

Most CFS uBiomes show high diversity — but CFS can be a progressive condition which would imply that the uBiome can change it’s profile over time.

Patient History

  • A year of antibiotics for a prostate infection was the probable cause
  • Fatigue, tendonosis, exercise fatigue, muscle twitching, dry eyes, joint pain, ibs, mcs.  The worst of which is the fatigue.
  • What helps:
    • Tai chi,
    • Sleep,
    • Equilibrium,
    • Align (B. infantis),
    • Amino acids (Tyrosine in particular),
    • 5htp,
    • Vitamin D (but causes sleep problems, so can’t take),
    • Regactive [Lactobacillus Fermentum (but causes sleep problems–probably the b vitamins?),
    • cocoa powder,
    • low starch diet (helps with pain, but carbs give more energy so I avoid most carbs and live with the lower energy).
    • Mutaflor helps but can make sleepy.
    • Bifido strains make sleepy.
    • L. Acidophilus makes dry eye worse.
  • State:
    • I would say that I’ve recovered about 40%, which has allowed me to work every day but hasn’t allowed me to have the energy to socialize, exercise or stand for long periods of time.
    • My IBS symptoms have been cured, however.

Basic Criteria for CFS/FM

E.Coli’s Parent:

Conclusion: Every basic criteria is a match. The low diversity is not typical but has been seen in some other uBiomes.

Overgrowth of Bacteria Genus

High

Rare Bacteria

Analysis of Over Growth

  1. Holdemania (genus) 
  2. Bacteroides (genus) 
  3. Akkermansia (genus) 
  4. Lachnospira (genus) 
  5. Bilophila (genus) 
  6. Anaerotruncus (genus) 
  7. Bacillus (genus) 

Items struck out below appear on both inhibits and enhances — so a toss up!

NUTRIENTS/ SUBSTRATES

INHIBITED BY

ENHANCED BY

INHIBITS

Bottom Line

My first question was why was there low diversity, there is no report of taking antibiotics? A good night sleep revealed the probable cause – because the right probiotic to reduce the high diversity was taken. The one that I suspect most as being the cause was:

  • RegActiv (Lactobacillus Fermentum)
    • “Up to the present no strain of lactobacilli with an extensive anti-microbial effect against numerous pathogens and opportunistic pathogens has been described.” – this one does!!!!
    • “The innate resistance of Lactobacillus fermentum ME-3 against antimicrobial preparations (TMP-SMX, ofloxacin, aztreonam, cefoxitin and metronidazole) allows to use it as a preparation accompanying antibiotic treatment in case of gastrointestinal and uroinfections”
    • Mutaflor is also possible, but seems less probable.

Wish List: Some patient with high diversity in uBiome try Lactobacillus Fermentum for 4-6 weeks and then get another uBiome done. This will provide some evidence if the above speculation is correct. If it is, then we may have discovered a key probiotic for remission.

Unexpected Scattering

Usually I have seen clustering (multiples) of some items across the bacteria genus. In this case, there is little, what there is:

One interpretation of the lack of clustering in the overgrowth is that the microbiome is moving towards normal. The highest overgrowth is just 2.74x well below most CFS uBiome results.

Patient Reports

I suspect that the sleepiness is a form of herx. RegActiv (Lactobacillus Fermentum) produced strong antibiotics and does Mutaflor. If there is an opportunity to take a week+ off from work for a ‘sleep vacation’, I would suggest loading up on one of them to try to the corner (but do not take together — they will disagree with each other). I recalled sleeping 12-14 hrs a day during my second episode from antibiotics for a few weeks, then it stopped.

An alternative would be to use Symbioflor-2 (US Source, World Wide Source) , another E.Coli probiotic and slowly work up the dosage – balance the dosage with the amount of sleepiness.

Dry eye: I have had dry mouth, and found that mastic gum cleared it up within a few days (not permanently). A reader provided an interesting comment on an earlier post:

“a treatment I developed for myself decades ago. During my late teens and early twenties I suffered from chronic ear infections. I eventually discovered that if I broke open an acidophilus capsule and left the contents between my cheek and gum overnight after brushing my teeth when I first felt an infection coming on, it would be cleared up by morning. Eventually, after a couple of years, I noticed that I no longer suffered from chronic ear infections.”

  • A very unorthodox approach (definitely needs medical review) is to use Symbioflor-1 or Symbioflor-2 as eye drops….

CAUTION: With prescription antibiotics, if you stop then the herx effect disappears within 24 hrs. With bioactive antibiotics (i.e. probiotics), a herx can go on for weeks. See this patient experience post and also this post.

As always, this is strictly an informational/education post of items that should be discussed with your knowledgeable medical professional before starting.

uBiome from a SIBO patient

A SIBO patient shared with me their uBiome results. Before I look at them I will state a question that I have:

  • Is SIBO substantially the same dysfunction but the person’s DNA can handle it without CFS or FM symptoms? We know that many symptoms are associated with specific SNP for both syndromes….

Patient Background

“After a bad case of food poisoning, I ended up with SIBO. The food poisoning was from campylobacter which produces the cdtb toxin…In my case of SIBO, it was caused by an autoimmune response. Taking probiotics triggers SIBO symptoms but I know I need to fix this imbalance. I would love to hear your thoughts or you can wait until I get my second results (unless you have some probiotics to try before retesting).”

Basic Criteria for CFS/FM

SIBO

sibo1

Lowish  E.Coli

  • Not directly reported, but it parent is: Enterobacteriaceae  which is 13% of the reference group

What seems different from the usual CFS profile is that the Firmicutes/Bacteroidetes ration is effectively normal — a significant difference.

sibo2

  • Diversity: 59%ile – usually CFS is very high (95+%ile)

Overgrowth of Bacteria Genus

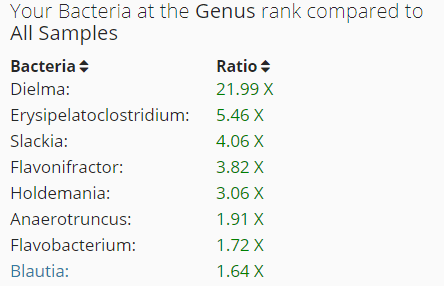
My criteria is to look at only those that are 1.5x or higher. We have only 2, a lot less than those seen in CFS/FM.

sibo5

Rare Bacteria

sibo3

Analysis of Over Growth

As usual, I head to datapunk.net to speed analysis (and allow folks to check or extend my research).

  1. Dielma (genus)
  2. Erysipelatoclostridium (genus)
  3. Slackia (genus)  – no info
  4. Holdemania (genus) 
  5. Anaerotruncus (genus) 
  6. Flavonifractor (genus) 
  7. Blautia (genus)  High
  8. Salmonella (genus) Rare
  9. Vagococcus (genus) Rare
  10. Delftia (genus)  Rare no info
  11. Citrobacter (genus) Rare

The numbers above are used below

NUTRIENTS/ SUBSTRATES


INHIBITED BY

ENHANCED BY

INHIBITS

Bottom-Line

This SIBO person has a uBiome very close to CFS/FM patients but with one, possibly critical, difference: Firmicutes/Bacteroidetes is normal. Also the diversity is normal.

While this is a single uBiome from SIBO without CFS, it suggests that the transition from SIBO to CFS may be caused by the Firmicutes/Bacteroidetes being lost; with this lost the equilibrium is gone and a ton of other bacteria genus can move in — pushing diversity to the top.

Suggestions for the patient to discuss with their medical professional:

Probiotics:  I would suggest trying at least one from each of the following two groups, I suspect the patients have done just the usual lactobacillus ones.

As always — for educational purpose only.


Hypothesis

SIBO is the lost of Bifido, Lactobacillus, E.Coli without a loss of the Firmicutes/Bacteroidetes balance and without the blossoming of additional species (i.e. normal diversity)

CFS is the lost of Bifido, Lactobacillus, E.Coli with a loss of the Firmicutes/Bacteroidetes balance and with the blossoming of additional species (i.e. high diversity)


Metronidazole – Dosages Review

Metronidazole/Flagyl is reported to have 75% of CFS patients improving according to some surveys. I was asked what is the best dosage…  that is for your MD to determine.

See this post to understand how it may be helping CFS — probably not how you think!.

MDs are busy people and often do not have time to check the recent literature. I’m busy too, but made time for this. My results (for educational purposes) are below

From Drugs.com with more details on Medscape.
drugs

Do any MDs use it for CFS?

  • Dr John E Tovey Consultant Pathologist in the British Medical Journal

    Article Related content Article metrics Rapid responses Response Chlamydia pneumoniae infection a treatable cause of Chronic Fatigue Syndrome The Editor British Medical Journal CHRONIC FATIGUE SYNDROME OR MYALGIC ENCEPHALOMYELITIS In your Editorial (BMJ 2007; 335: 411-2), relating to the NICE clinic…
    BMJ.COM

Bottom Line

There are no dosage studies or guidance for CFS/ME. From the above, I would conclude the following as a reasonable plan:

  • 400-500 mg three times a day for 14 days, followed by 200 mg/daily for at least 2 months.

NOTE: this applies to other antibiotics also
“Metronidazole can have cerebellar toxicity that manifests clinically with varying degrees of limb and gait ataxia and dysarthria (Table 2). Symptoms are accompanied by characteristic T2 high signal lesions on brain MRI in the cerebellum and brainstem. Neurotoxicity was seen after prolonged use of metronidazole with clinical symptoms resolving within 3–7 days of discontinuation of the medication, while follow-up MRIs also show resolution of cerebellar lesions [111]. While the precise mechanism for neurotoxicity is not entirely clear, one hypothesis is that it occurs via axonal swelling secondary to metronidazole-induced vasogenic oedema [112]. Peripheral neuropathy is another recognized potentially neurotoxic effect with use of metronidazole. One report describes a 53-year-old who developed encephalopathy, dysarthria, ataxia and a length-dependent peripheral neuropathy in the context of prolonged metronidazole therapy (a cumulative dose of 146 g over 88 days). Multiple skin biopsies confirmed evidence of a small fibre sensory neuropathy [113]. In another case reporting the rapid development of peripheral neuropathy related to metronidazole with electrophysiologic studies demonstrating prolonged distal motor latencies, mildly decreased compound muscle action potential and decreased sensory nerve action potentials involving the posterior tibial and peroneal nerves to varying degrees were noted [114]. Optic neuropathy, as well as autonomic neuropathy, have also been described in association with metronidazole use [115, 116]. Other neurological adverse effects ascribed to metronidazole include dizziness, headache and confusion [117].” 2011

Again, not medical advise, just a summary of the literature and conclusions from the literature for educational purposes. Applicability to individuals need to be done by a qualified medical professional who knows your medical history.

A Third Bioscreen Report with Patient Experiences

A reader wrote with some specific questions and shared her BioScreen report. I will first do my standard review and then address the questions. Remember, I am not a medical professional — more a librarian who knows how to lookup things, read things (ex-technical writer) and apply logic.

Basics Criteria

dc1

dc2

And as usual, their automated comments on each, for example:

dc3

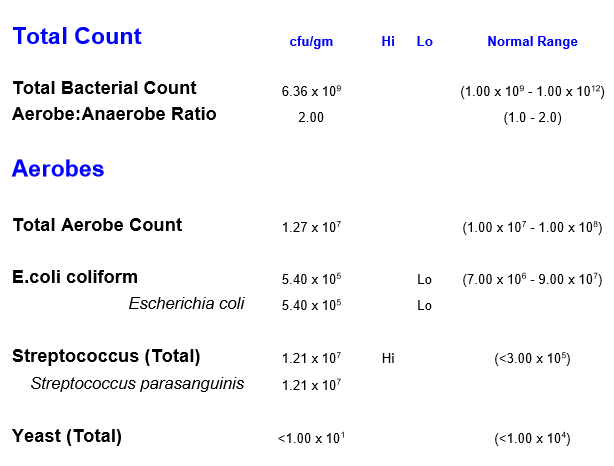
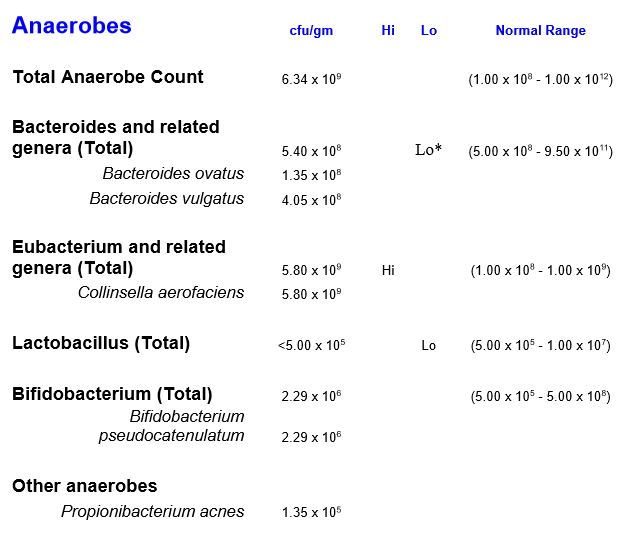
  • Low E.coli – as expected
  • Low Lactobacillus – as expected
  • Normal Bifidobacteria — BUT only one species.. i.e. all of the other species are missing!

Analysis of Over Growth

As usual, I head to datapunk.net to speed analysis (and allow folks to check or extend my research).

  1. Bifidobacterium pseudocatenulatum (species) Note: I deem this to be an overgrowth, because it is the only bifidobacterium!
  2. Streptococcus parasanguinis (species) 
  3. Collinsella aerofaciens (species) 
  4. Propionibacterium acnes (species)  I included this because it was there with no reference levels — i.e. unexpected growth!

Note: [Parent] below indicates that it applies to bifidobacterium and not this specific species (which we know nothing specific about)

NUTRIENTS/ SUBSTRATES

INHIBITED BY

ENHANCED BY

INHIBITS

Questions and attempted answers


Q:  My main overgrowth is Streptococcus Parasanguinis, I believe this lives in the mouth and is normally killed by the stomach acid. Does this automatically mean that  I have low stomach acid, and if so, this problem can not be repaired until the stomach acid issue it cleared. Or could it be that the strain I have has somehow adapted to with stand the acid in the stomach. I have also read somewhere that people with CFS can not produce enough stomach acid due to the high amount of energy required to do so, what are your thoughts. Is this strain of Strep overgrowth common?

A: DataPunk cites ” The presence of S. parasanguinis in the oral cavity is associated with a healthy microflora. Identified as a constituent of the oral microbiome by Human Oral Microbiome Database. Identified as constituent of vaginal microbiome. [PMID:23282177]”

There are a large number of potential cooking items listed above that should suppress it in the gut. These include:


Q: Do you recommend antibiotics, rather than herbs for my situation, if so which ones.

A: I always prefer non-antibiotics as the first choice. Antibiotics tend to have cascading side effects (‘casting out a demon from the house, and a dozen more takes it place’ syndrome). If you go the antibiotic route — make sure that you are not given an antibiotic that worked when your MD went to Medical School and is ineffectual now (See this search)

Q:  I also have a parasite (Blastocystis) which I believe this is very difficult to get rid off and requires multiple antibiotics. My thoughts are to ignore this for now until the bacteria is in a better place and then readdress it. What would your advise be?


A: I checked PubMed and found some studies of interest

Q:  I have had a bad herx from Prescription assist (dizziness, spaciness, bloating) however by the time I finished the 1st bottle I as able to take two caps per day and was feeling much better (no herx.)

A: Thank you for sharing! A herx can happen — my two worst were from Mutaflor and Lactobacillus Fermentum ME-3. As with you, the herx disappeared and I felt a lot better afterwards!

Q: I have just started on symbio 2. I started on one drop and by day three was up to the standard dose as I had no herx & felt a huge improvement in all my symptoms and energy (the best I’ve felt for months). Can you confirm that we need to take both Symbio 2 and Mutaflor or just one or the other? 

A: My own opinion is that if there is not an economic issue, do both. Symbioflor-2 standard dose is much less than Mutaflor standard dose (which is why I like suggesting using Symbioflor-2 to start). They are different strains.

Q: . I took a low dose of thyme and rosemary oil as an antibiotic, Interestingly my blood pressure dropped and I experienced POTS. These are CFS symptoms I have not experience for a few years since I started drinking liquorice tea daily in order to increase my blood pressure (which it did). I  wonder if bacteria affects blood pressure and causes POTS which a very common symptom in CFS.

A: There is a recent article that may answer that question:
The Microbiome and Blood Pressure : Can Microbes Regulate Our Blood Pressure? [2017]  “Studies have described how dysbiosis may modulate blood pressure and contribute to CVD. ”

As always, consult with your knowledgeable medical professional before any changes — I do not know your medical history and not qualified to give medical advice. The above is educational only.


Treating Candida without Saccharomyces Boulardii

I had done a detail post on Saccharomyces boulardii in 2016 and concluded Do not explicitly take this probiotic. Looking at the overgrowth of several bacteria genus in uBiome samples from CFS patients, I keep finding this listed as enhancing the overgrowth bacteria.  Almost all of these overgrowth bacteria suppresses bifidobacteria and thus appear to contribute to keeping supporting the CFS microbiome state.

Molecular Monitoring of the Fecal Microbiota of Healthy Human Subjects during Administration of Lactulose and Saccharomyces boulardii [2006] found no impact on bifidobacteria but reading the study we read “”None of the subjects had a history of gastrointestinal or metabolic disease” as well as  “it cannot be excluded that subtle changes in less predominant species or groups of species may remain undetected by this approach.” On both of these grounds, their conclusions likely do not apply to dysfunction when rare bacteria take over; bacteria that are our overgrowth.

What should be considered as alternatives?

Bottom Line

Many things work against candida. Some researcher are happy to publish positive results that it reduces candida by 50% (1/2). When actual numbers are given, we want the one(s) with the best numbers. The clear winner is: Lactobacillus Fermentum reducing to 1/10000. This is available on Amazon.com in 6 BCFU capsules.The next one with numbers is Mutaflor, just reducing candida to 1/10.