Does a Ketogenic diet alters the microbiome in a good way for CFS?

A reader asked this question, and a summary of what we find in the literature is likely good. Whether it applies to you depends on what bacteria genus you are high in.

What is a [proper] ketogenic diet – The ketogenic diet is a high-fat, adequate-protein, low-carbohydrate diet [Wikipedia]. It was first used in the 1920s, “outside of paediatric epilepsy, use of the ketogenic diet remains at the research stage“.

  • “A recent study by our group has demonstrated that a brief ketogenic period, if followed by a longer period of correct Mediterranean diet could avoid this yo-yo effect” (Paoli et al., 2013)
  • “This rapid and marked expansion in the representation of the Bacteroidetes, achieved after a 24-h fast,” [2009]
    • “fasting was associated with a significant increase in the proportional representation of the Bacteroidetes [from 20.6% (fed) to 42.3%”
    • “A ketogenic diet did not produce a notable change in the ratio of Bacteroidetes to Firmicutes in the cecal microbiota compared with CARB-fed, untrained (or trained) controls (Fig. S2C). However, unlike fasting, a ketogenic diet was associated with a significant decrease in bacterial diversity (P < 0.001; Fig. S2A). “
  • “KD reversed the elevated Akkermansia muciniphila content in the cecal and fecal matter of BTBR animals.” [2016]  – only a subset of CFS patients have high Akkermansia, most are low. [2016]

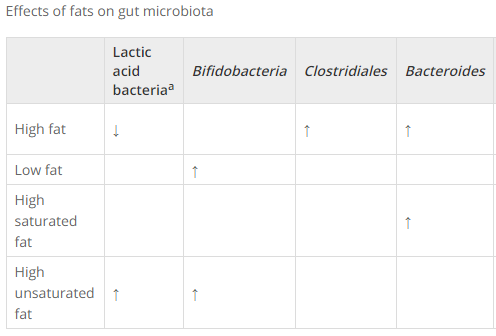
    • According to the above chart — Bifidobacteria is lowest on K.D.
  • Lactobacillus and Bifidobacteria decreases over time on a low-carbohydrate high fat diet. [2009]
    • Lactobacillus and Bifidobacteria increase over time with high carbohydrate, low fat diet.
  • “In contrast, the Roseburia spp. and Eubacterium rectalesubgroup of cluster XIVa and bifidobacteria decreased as carbohydrate intake decreased. ” [2006]

Bottom Line

With repeated studies finding a decrease of bifidobacteria and lactobacillus with a Ketogenic diet, I do not believe it has any clear benefit and may encourage further negative shifts with some CFS/IBS/FM patients.

CFS Patients appear to universally have very low or zero bifidobacteria, lactobacillus.


There are no official tests for CFS — but there are a ton of markers!

I often have read on the web that there is no test for CFS. This is very incorrect — there is no official test for CFS nicely bundled up.  “No current diagnostic tool or method has been adequately tested to identify patients when diagnostic uncertainty exists.”[2014]  What we find in the literature are many tests available to confirm CFS/ME when symptoms presents.

This post reviews where there have been a strong association of abnormal laboratory results to CFS/ME patients. These tests can often be used to confirm that the diagnosis is correct. For example: is TGF-β elevated and resistin lower?  etc.  In terms of microbiome results from uBiome.com: low or no lactobacillus, low or no bifidobacteria, low or no akkermansia muciniphila, low or no E.Coli.

My Own Favorite Ad-Hoc Markers

From uBiome:

  • Low or no Lactobacillus
  • Low or no Bifidobacteria
  • Low or no E.Coli
    • Not directly reported, but it parent is: Enterobacteriaceae which will be NOT listed in results, or at something like 2% of the reference group
  • Low or High Akkermansia (parent is Verrucomicrobiaceae)

Bottom Line

Yes, there is testing that can be used to increase the certainty of a CFS/ME diagnosis (or exclude it — which should lead to further testing).


uBiome of a MCS with CFS person

I am working on a post on MCS and the microbiome. If you have MCS, uBiome results and willing to share your login for a week, please email me at Ken [at] Lassesen.com. During one episode with CFS, I had mild MCS which resolved with remission — this cause me to suspect that there is a significant microbiome aspect to this condition.

Patient Profile

  • CMV epidemic and a mono-like illness may have been the triggering event
  • IBS for 20 years, disappeared 14 years ago (may have been replaced by MCS 😦 )
  • CFS for 25 years
  • MCS for 15 years

“I have improved from whey (Immunocal, ImmunoPro / VitalWhey), especially in MCS, begun at age 47. It is the only substance that has ever impacted the MCS. In terms of the CFS, however, I feel whey is propping me up to be capable of the minimal activity involved in taking care of myself, but that it is not curing. It feels as if I am gradually running out of steam.”

“In 2014, I tried:

  • Neem leaf (abandoned after two days: gut distress, migraine, and intolerable hangover);
  • Gerber Soothe Colic Drops L. reuteri (abdominal pain, gas);
  • Securil Propio-Fidus P. freudenreichii (migraines, smelly poop);
  • Ultimate Flora RTS Colon Care bifidobacteria (no clear result).”

Standard Checks

Doing my standard verification (pattern reported since 1998!):

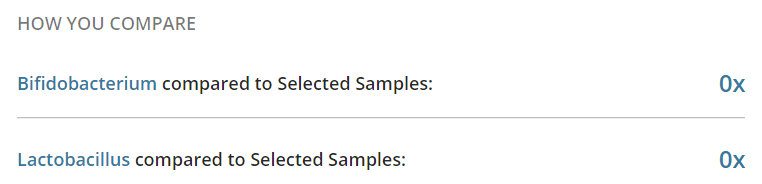
  • Zero Bifibobacterium
  • Zero Lactobacillus
  • Zero  Akkermansia  (none reported)
  • E. Coli is very likely zero
  • Diversity: 47%ile (i.e. “normal”)

Grand Slam!

aero

rare1

overgenus

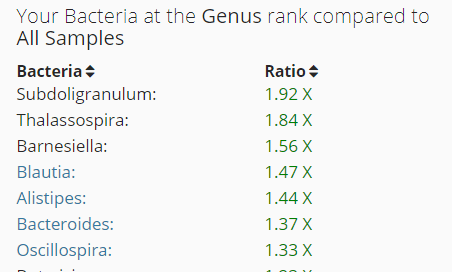
  • There have been just 3 other uBiome with high Subdoligranulum.
    • Two of them are also high in Thalassospira (with only 3 being high)
    • None are also high in Barnesiella
    • All are also high in Blautia (about 50% are high)

Analysis

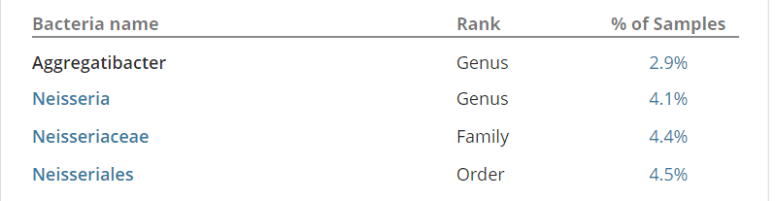
The Neisseriales order – we do not know it’s KEGG pathways (or much more about it) (from DataPunk). Only 1 other uBiome have any Neisseriales — based on the frequency of MCS with CFS, I would conclude that this is noise and is not MCS connected (and likely not CFS or IBS connected).

This leaves the following:

  1. Subdoligranulum
  2. Thalassospira
  3. Barnesiella
  4. Blautia
  5. Alistipes

Looking at what is known to inhibits these

And the flip side, enhanced (we do not want!)

All of these genus are known to inhibit bifidobacteria (note: some bifidobacteria are known to inhibit other bifidobacteria — it is not one happy genus!), and bifidobacteria is known to inhibit all of the above.

Suggested Initial course of action

The following are known to increase bifidobacteria (see link above)

Because of her issue cited above, I would suggest the following moderate change of daily diet:

BEWARE of Saccharomyces boulardii in yogurt and other products. You want to avoid.

Resistant starch: You want type III and to eliminate II (i.e.  high amylose corn starch) and IV (“hi-maize resistant starch.”). See this post on another site.

I would suggest resuming with Ultimate Flora RTS Colon Care bifidobacteria, or other pure bifidobacteria products, see this post for relative costs. You may wish to try one box of Align (since it is a specific strain and is well documented). If the above goes well, then consider adding Prescript Assist or/and Equilibrium in.

As always, discuss changes with your knowledgeable medical professional.

Bottom Line

This is a long term CFS/MCS with a touch of IBS patient. who reacts adversely to several things. Altering diet to be unfriendly to overgrowth and supportive of undergrowth is likely a good starting point. Thanks to DataPunk, I was able to assemble lists of foods and supplements that are known to impact these bacteria.

Food to Increase Bifidobacteria and Lactobacillus

I generally recommend against taking Lactobacillus probiotics. There are two reasons:

  • They will not repopulate your microbiome — they will be rejected just like an organ transplant. Most are eliminated in a few hours and literally nothing is found the next day.
  • They produce metabolites and antibacterials which will often suppress populations that you are low in.

On the flip side, I am in favor of feeding your native lactobacillus and bifidobacterium.  The question is what helps them to grow????

LATEST INFORMATION (Constantly being updated)

There have been many studies on ITF,FOS,GOS etc, but results tend to be inconclusive [British Journal of Nutrition review]

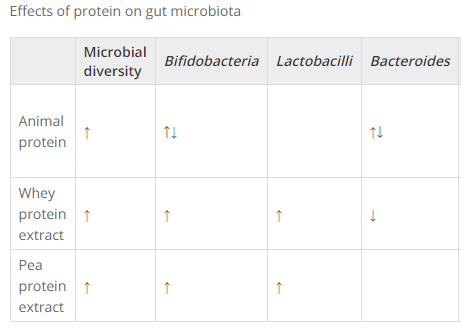
I came across this 2017 study which compare the impact of three different types of protein source on bacteria.

The first table is shown below. It is very interesting because back in 2000 there was great interest and many reports of improvement. The thinking then was that it helped by providing glutathine levels [see Dr Cheney’s note from Oct’1999]. It seems that there may be an additional/alternative mechanism involved: increasing lactobacill and bifidobacteria (something off the radar of researchers back then)!

whgey
  • ” Whey milk had a strong prebiotic effect on the gut microbiota …, showing a significant increase of Bifidobacterium (p < 0.05) with cow, sheep and mixed whey and increase in the Lactobacillus group, ” [2017]

The second table is interesting because it does not list lactobacilli but lactic acid bacteria. Bacteria that produce lactic acid (which appears to be high with CFS patients).

fat

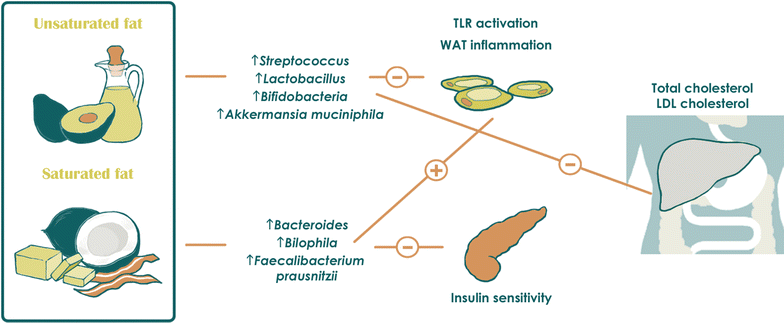
A visual may help:

12967_2017_1175_fig3_html

Pea Protein

Pea is a pulse which I have mentioned before.

  • “DNA microarray results suggested that feeding Pea Fiber diet inhibited 77% of genes (40 downregulated and 12 upregulated genes) related to colonic cancer, immune response, and lipid metabolism, involving in signal pathway such as intestinal immune network for IgA production, peroxisome proliferator-activated receptor signaling pathway and nutrient metabolism-related pathways. ” [2014]
  • ” The glycated pea proteins affected the growth of gut commensal bacteria, particularly lactobacilli and bifidobacteria, whose levels increased significantly.” [2011]
  • “The Firmicutes/Bacteroidetes ratio was reduced with oligofructose , yellow pea fiber , and yellow pea flour” [2014]
  • “Pea Fiber significantly decreased the plasma levels of isoleucine, leucine, lactate, and pyruvate as well as the urine levels of allantoin, bile acids, and trigonelline. Wheat bran Fibre significantly increased the plasma levels of acetone, isobutyrate, lactate, myo-inositol, and lipids as well as the urine levels of alanine, lactate, dimethylglycine, N-methylniconamide, and α-ketoglutarate. ” [2014]

Bottom Line

I have written about whey before (as source of Glutamine[2015]) and  Whey, Colostrum and Goat Milk June 2017. Today, we need to look at Whey as the ideal food to increase Lactobacillus and Bifidobacteria.

IMPORTANT: We are talking about cow, sheep whey NOT soy whey or vegetable whey. We want the simplest ingredient list for it (no favoring or additives). Beware of  Emulsifiers! Examples (not a recommendations) Wild Whey (from Australia)
, Naked Whey, and the favorite back in 1999, Imunopro.

Did whey cure anyone back in 1999? My memory is that there were a few that improved sufficiently to return to work, many that found some improvement, and a few that reported no effect. IMHO, the bad (overgrowth) bacteria need to be reduced concurrent with whey supplementation. Whey is not a cure by itself, it is fertilizer to help remission.

Treatment options for a uBiome Subset

In an earlier post, a reader had a uBiome result high in:

Another uBiome is similar:

lala

This pattern occurs in around 25-30% of CFS patients uBiome result, i.e. a subset. All of these are butyrate producers which suggest that Miyarisan (Clostridium butyricum) should not be taken – based on the belief that butyrate producers cross support each other.

And I found a study that described what will increase it, the logical thing is to do an anti-diet based on this diet. Unfortunately, brain fog is a challenge for many CFS patients, so I will attempt to extract and expand details on how this could be reduced.

  • “Adding meat back in to a vegan diet caused an immediate increase in the bacteria (Bilophila wadsworthia, Alistipes putredinis and species in the genus Bacteroides) that grow with exposure to bile, which increases when a person eats more fat.” [From Nature]

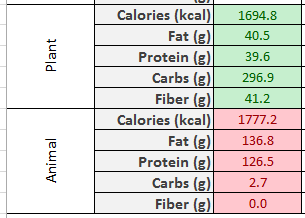
In terms of the usual things people count in a diet, the table below green shows where you should want to end up. The red numbers are what you do not want to have. The more you shift to the green, the better — but do not get dogmatic about doing exactly the green.

diet

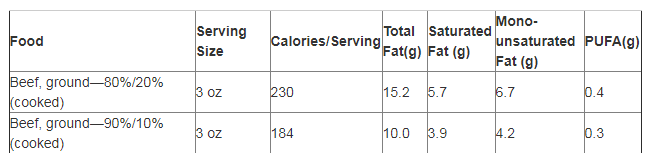
See this chart for help in knowing what the fat content is of meats:
fat

  • Alistipes
    • butyrate & histamine producer [src]
    • “Alistipes putredinis, and Eggerthella spp. were associated with cruciferous vegetable intake” [2009]
    • Resistant to Vancomycin, Kanamycin, Colistin [2006]
    • ” is susceptible to penicillin G, imipeneme, amoxicillin + clavulanic acid and clindamycin but resistant to metronidazole and vancomycin.” [2012]
  • Bilophila
    • penicillin resistant [src]
    • butyrate & histamine producer [src]
    • Increases with High saturated fat [2017]
    • “Clindamycin showed antimicrobial activity by all methods,” [1998]
    • ” Bilophila wadsworthia indicated significant resistance to several beta-lactam antibiotics, including imipenem and cefoxitin. ” [1992]
    • “Promote pro-inflammatory TH1 immunity” [2017]
    • ” only metronidazole was uniformly bactericidal” [1993]
      • “With chloramphenicol, some Bilophila strains tested showed regrowth starting at 30 hours. Several strains of B. gracilis were not killed by ampicillin/sulbactam, clindamycin, or cefoxitin. Activity was variable among strains and antimicrobial agents.”
  • Oscillospira
    •  butyrate producer [2017]
    • butyrate & histamine producer [src]
    • Increases on a high fat diet[2015]
    • Oscillospira bacteraemia(infection) can result in: [2014]
      • below average temperature (35.6C, 96.1F)
      • low blood pressure (70/50 mm Hg)
      • high c-reactive protein
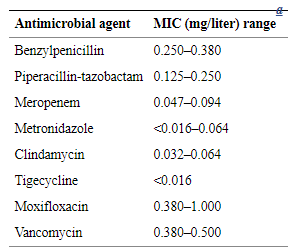
    • Antimicrobial sensitive [2014] – smaller is better
      anti
  • Butyricimonas
    • butyrate & histamine producer [src]
    • “sensitivity to ampicillin, sulbactam-ampicillin, amoxicillin-clavulanic acid, piperacillin-tazobactam, imipenem, meropenem, clindamycin and metronidazole.” [2015]
    • Butyricimonas bacteraemia (infection) can result in [2016]
      • Below normal temperature
      • Subjective fevers
      • headaches and chills
      • gastrointestinal malignancy common
  • Gordonibacter
    • diet with stearic acid  decreases [2013]
    • butyrate & histamine producer [src]

Update

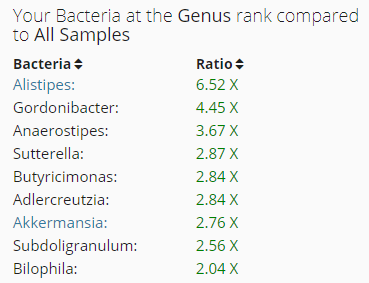
I decided to add more information (now that I have found a good information source) to the above example and expanded it to all genus > 140%:

  1. Alistipes
  2. Gordonibacter
  3. Anaerostipes
  4. Sutterella
  5. Butyricimonas
  6. Adlercreutzia
  7. Akkermansia
  8. Subdoligranulum
  9. Bilophila
  10. Pseudobutyrivibrio
  11. Gelria  nothing known

Inhibited By (Desired for this patient)


Enhanced By (this patient should avoid)


Inhibits:

  • Bifidobacterium – 1, 3, 5, 6, 7, 8, 9, 10

Cavaet

The above is based on our current knowledge which is very incomplete.

Bottom Line

It was interesting to note that two of these bacteria results in subnormal temperatures with bacteraemia. This is of special interest because CFS patients often have subnormal temperatures. This may be just a coincidence, or may indicate why it is seen in some patients.

Most of them are butyrate producers, histamine producers and inhibits birifobacterium! OUCH! It is known that a significant subset of CFS patients suffer from D-Lactic Acidosis (too much lactic acid).  There may be another subset that suffers from too much butyrate (butyric acid).

In terms of treatment, diet change would be my first choice. Second choice would likely be metronidazole because 3/5 bacteria are known to be sensitive to it. For herbs and spices, there is nothing (which is not surprising because these are all recently identified bacteria).

As always, consult with a knowledgable medical professional.