uBiome from an improving adult

This weekend I received this email from a reader (quoted in full — as received):

Hi Ken, 

I was wondering if you would be willing to review my uBiome sample and provide me some feedback.  Feel free to share my results on your website. To give you a little bit of background, I have been diagnosed with IBS and more recently CFS.  My mothers side of the family has a lot of GI issues.  Half (7/14) have been diagnosed with IBS or Crohns with some having very serious cases of Crohns.  

Back in March I had to take time off work because my energy levels were so low that I could barely do anything.  During that time I followed many of your suggestions on herbs and probiotics.  I cycled through the following probiotics: Mutaflor (I could not take this for very long as it gave me bad stomach pain), Symbioflor 1 and 2, Prescript Assist, GB Equilibrium, L fermentum ME3, AOR-3 and Align. The only ones that produced any herx were PA and Symbioflor 2 and they produced fairly significant herx.  I did have minor herx while I was taking Align, AOR-3 and GB together in large amounts but it didn’t last very long, only a couple days.. The herbs I tried were: Neem, Tulsi, Oil of Oregano, harataki, coconut oil, licorice, turmeric and olive leaf. I had some herx from Neem, Tulsi and licorice but it was very little and only lasted for a couple days for each.  I increased the doses quite a bit but still got no added herx.  When all of these probiotics and herbs no longer had any effect on me, I stopped taking them.  Since then my energy levels have improved significantly where I am now able to work again.  Thank you so much!  I honestly can’t thank you enough because I really do feel like you have saved my life.  I have been to the mayo clinic, nutritionists, naturopaths, I have done an all liquid Vivonex diet, FODMAPS, quit sugar, gluten, alcohol, dairy and carbs, etc. etc.  My wife and I have easily spent over $25 000 to try to improve my condition in the past three years. 

Prior to taking these probiotics I was extremely gluten sensitive.  A few years ago, at the suggestion of a nutritionist I quit eating gluten.  Only four days after quitting, I accidentally ate some gluten and I got extremely sick.  Within 10 minutes, my stomach bloated out an extra 3 inches, I got a really bad headache, lightheaded and dizzy, really bad stomach ache, my skin got really dry, I got really depressed and I started to dry heave.  This happened every subsequent time I accidentally had gluten.  Last month I accidentally had gluten and nothing happened. I am now able to eat gluten.  I think this really hits home to your post earlier in the week about how the person isn’t gluten sensitive but their microbiome is.  Sorry if I’m going off on a tangent but I thought you might find this information interesting.  I would not consider myself in remission because I still have bad days and even my good days I feel like I’m only about 75-80% but this is such an improvement that I feel like I have my life back.  I was wondering if you would consider having a look at my results and offering any opinions on where I could improve my gut bacteria so I could potentially further improve my condition.  

uBiome Result Review

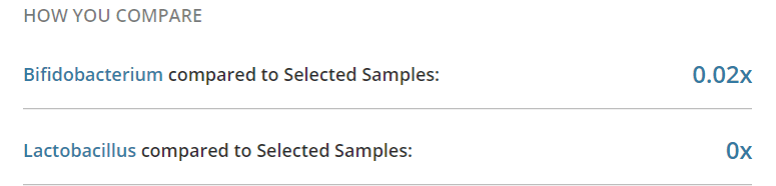
Despite the probiotics, the classic two items are still low:
canada

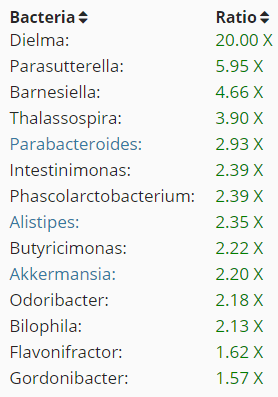
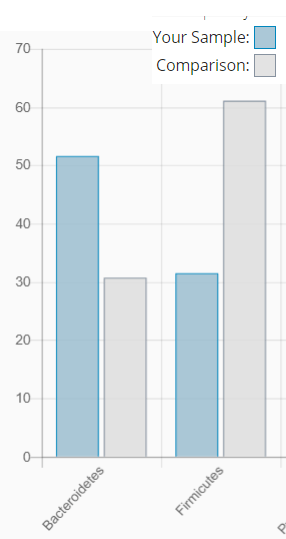
Akkermansia was 220% of typical results. The ratio of Bacteroidetes to Firmicutes is still far from normal.
firmbact

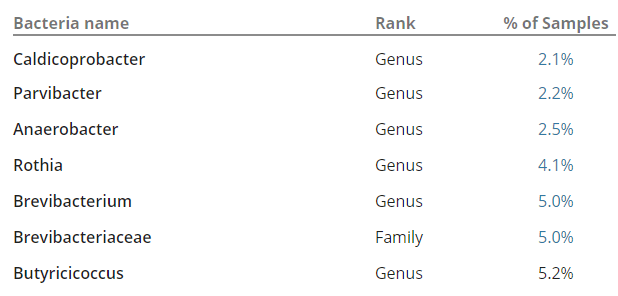
As seems to be common, biodiversity is high (88%ile) – but less than many uBiomes that I have seen. In terms of most uncommon bacteria (i.e. < 5% of sample), his is lower than is usually seen, a good sign. Note all of these are less than 2% of the level found in those that have these bacteria.

rare

The Candidatus Saccharibacteria is very interesting because it has a parasitic phase (killing it host bacteria) and has been isolated from the human oral cavity.

  • It “associated with human diseases such as periodontitis and inflammatory bowel disease (IBD) ” [2014]
  • It may be reduce by Azithromycin [2016]
    • Hint: if you want to go the antibiotic path, you may find dentists are more cooperative than many MDs… if it is for periodontitis issues [do not oversupply information].
  • It is involved in many many KEGG pathways (see site)

Oribacterium is also found in the human oral cavity. [2014] “Susceptible to kanamycin, vancomycin, metronidazole, penicillin, rifampicin and bile but resistant to colistin.”

Concern: while there are low in the gut results, the usual origins of them are the oral cavity suggesting that there may be an overgrowth of there there.

Overgrowths
class

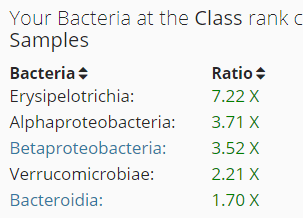
Erysipelotrichia appears to increase with high fat diet [2011] [2017], so reducing fat intake —  reduce beef and pork, increase chicken, turkey and rabbit. Alphaproteobacteria is also associated with high fat diet [2015]. Betaproteobacteria is associated with diabetes risk [2012].
order

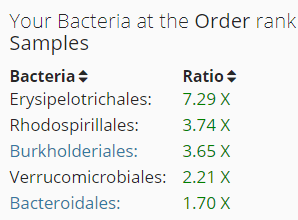
Again, all of high ones were associated with high fat intake.
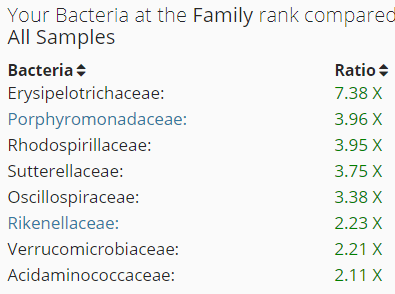
family

genus

Dielma (part of Clostridiaceae bacterium) is of special concern, unfortunately I could find nothing specific for diet. ” D. fastidiosa is susceptible to amoxicillin, imipenem, metronidazole and ciprofloxacin, but resistant to trimethoprim/sulfamethoxazole, rifampin, doxycycline and gentamicin.” [2013] Based on CFS patients reports listed here, I would seek a course of metronidazole,  followed by a course of ciprofloxacin (a fluoroquinolones) from my MD (actually a ND in my case).

Bottom Line

This person has seen some dramatic changes. From becoming gluten sensitive to being able to consume gluten again. From being unable to work, to returning to work. His uBiome is reasonable for 70% recovery. It is not as good as the last uBiome review where the person felt that he had effectively recovered.

Using the model, he has successfully suppressed many of the bacteria that was causing symptoms. The very important word is suppressed – not eliminated. My view of the “bad bacteria” is that they should be thought of as a virus. You never eliminate the virus, rather your system learns to keep it in control.

I would advocate continued rotation of herbs and probiotics for at least 6 months. I still rotate them – I keep a cup of triphala or neem tea; I usually take one probiotic for a one week cycle. If I forget, I do not get uptight about it. However, whenever I get anything suggesting stomach upset or a cold or flu… then I load up quickly (which seems to have the additional benefit of shortening the duration).

Discussion with their MD on getting the two candidate antibiotics cited above is recommended. As always, always discuss any changes with your knowledgeable medical professional.
uBiome sample from a recovering young person with CFS

This uBiome was different than others — age may be a factor dealing with microbiome shifts in CFS.

Short History of Key Points

  1. Original Onset appear to have been triggered by an amalgam being removed in grade 12
  2. Subsequent was sinus infection etc with likely an inappropriate antibiotics for this person
  3. Repeat when the amalgam was replaced again a year later
  4. At university, the dorm he was in appear to have had significant mold issue
    1. fresh fruit would go moldy in 1-2 days constantly
    2. room mate with autoimmune issues was having constant flares
  5. Today, he is back at university in a different dorm (does not appear to have mold issues)
    1. Has been doing variety of herbs etc that been suggested on this blog over this year
    2. Greatly improved compared to the last few years
    3. No stomach or digestive issues at present
    4. This uBiome was done in the last few weeks (his current state)

“Interestingly enough, I’ve also had a higher precedence of cavities since college started and they only got worse when my symptoms of fatigue began as well”

Current Status

Unlike most CFS patients, the ratio of Firmicutes to Bacteroidetes was close to normal.

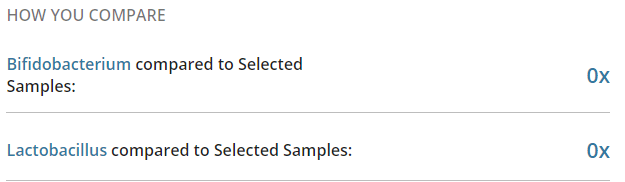
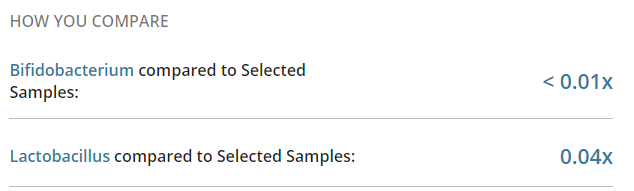
  • Bifidobacterium was 61% of normal
  • Lactobacillus was < 1% of normal
  • Akkermansia – none reported.

At the Genus level, there were several abnormal high:

  • Collinsella: 263% of normal (high seen in 25%)
  • Enterorhabdus: 326% of normal (only rarely seen)
  • Intestinibacter: 241% of normal (high seen in ~50%)
  • Roseburia: 247% of normal (high seen in 30%)

What do we find:

  • Collinsella and Enterorhabdus are reduced with smokers with Crohn’s Disease [2016]
  • “A lower abundance of Roseburia has been observed in patients suffering from inflammatory bowel disease.” [ubiome]
  • Higher level seen with diets with whole grain [2013]
  •  Metformin will “increases Escherichia and lowers Intestinibacter abundance” [2015]
    • “elevated levels of Roseburia may be associated with weight loss and reduced glucose intolerance.” [ubiome]

Pre-diabetic?

Looking at some articles, there is a possibility that being pre-diabetic may be a factor (hint: testing should be considered).  A pre-diabetic diet should be consider – see this WebMD page. Diabetes does run in his family.

Analysis

This reader abnormalities do not have any association with IBD etc. His values were high when a low value was associated. The uBiome agrees with his symptoms.

I was at my dentist recently and she gave me a list of supplements that help with dental gum health (will do a post on this) which almost looks like it was written for CFS patients — the same items occur constantly. One of my own crowns is a concern to her because the x-rays are unclear if I have grown a colony of bacteria under the crown (a location very hard to treat with antibiotics, but also a location which could re-infect the body). She was recommending removing the crown and send samples for analysis.

For amalgams, the traditional view has been the mercury has created health issues. There is an alternative explanation, the area under the amalgam may be an ideal colony site for some types of bacteria; bacteria that could be release slowly or in quantity when dental works occurs. This reader appear to have suffered multiple insults: Amalgam-bacteria onset, antibiotics that further shifted his microbiome, prolonged mold exposure adding more shifting of his microbiome.  He is getting his mouth into better shape, he found brushing with Alpha-Lipotic Acid helped his mouth(I love readers sharing successful experiments!) . His mouth appears to be a key source for his CFS.

Fortunately, he appears by symptoms and ubiome to be on his way to recovery.

Bottom Line

My usual criteria for probable CFS using uBiome is having two of the following three very low:

  • Bifidobacterium
  • Lactobacillus
  • Akkermansia

This uBiome made that criteria but not in the usual way. He appears to be on the way to recovery (but need to be wary of factors that could cause flares or worst)

  • The glucose/diabetes related issues hints that Lactobacillus Fermentum ME-3 should be tried. [2014][2016]
    • Consider breaking a capsule apart and leave the contents in your mouth for a while after brushing your teeth
    • You may wish to try this with other probiotics.
  • The chewing of various natural gums (myrrh, mastic, boswellia) should also be considered because of the dental issues (and the potential of the mouth being a reserve to re-introduce bacteria into the guts).
    • Do a variety of oral probiotics
  • Do appropriate herbal teas: Triphala, Neem, etc — we want their contents to hang out in your mouth area.
  • Redo uBiome in December to see what shifts has occurred

As always, consult with a knowledgeable medical professional before adding or changing supplements.


Post #700 – Roles in Treating CFS

This is my 700th post and at the same time, a reader asked

“Ken I’m writing my final degree project in CFS and I would like to know, in some phrases, what you think about the role of “official medicine” in the treatment of the disease.
What’s your goal with the blog and how it can help the patients”

Role of Official Medicine

I need to answer this based on my model and observations. Medicine is looking for simple cookbook solutions to a complex condition. Most practicing MDs are also greatly constrained by several nasty things:

  • “Standards of Care” –  “Practice guidelines assist the health care practitioner with patient care decisions about appropriate diagnostic, therapeutic, or other clinical procedures for specific clinical circumstances.” [NIH]
  • “Medicare Insurance” – this is very closely tied to above
  • “Peer pressure” – What would other doctors do in their region.

A professor once told me: “The ideal doctor or engineer is the person with a fantastic memory, strong sense of conformity and zero creativity”.

Give them a cookbook on how to treat an issue by a medical association, and they will follow it. Give them a ton of studies with conflicting results and they will either say “We will wait until there is clarification” or “It is probably psychological or best handled by a specialist”. Often the excuse can become “We need more studies”…. studies that may never happen. Most MDs do not want their rear side exposed to fellow MDs, local medical organizations and insurance companies  for some very hard financial kicks.

Bottom Line: Official Medicine will stay in a holding pattern for years, likely decades. They will provide symptom relief and ad hoc  random experiments (often repeating things tried unsuccessfully decades ago!). Only an extreme few would read any research on CFS regularly.

Research

My opinion based on seeing enough studies is that CFS/FM/IBS symptoms are interactions between DNA/SNP and microbiome (which has more DNA than a human). The appropriate research approach would be to take a large sample of patients (likely 100,000 or more) and record:

  • DNA
  • Microbiome
  • Symptoms and Lab results

Then push all of this data in appropriate artificial intelligence algorithms to break down/discover the associations. In the comments of my last post,  you would see that I identified several bacteria groups that are very high. When the reader tried any suggested herbs, they became severely depressed in days and stopped. A little research on PubMed discovered that most of these bacteria groups are strongly associated with depression. The die-off from the herbs was triggering the depression. One type of symptom==> a group of bacteria (and likely DNA also).

Current Researchers

Most researchers are trained in specialties. They do excellent work examining the leaves and twigs around their focus of interest.  The problem with CFS is that the issue is bigger, not just the branches of the tree or the whole tree — rather the entire forest. IMHO, an ideal CFS researcher would be trained in medicine, DNA/SNP, microbiology and machine learning. They would need to be a world class data scientist besides being an MD. They will also need a big budget and cooperative clinics to get an adequate data sample (I am talking 100,000 patients needing their DNA and microbiome done).

To me, one of the greatest problems with CFS research is that successful results from studies are rarely repeated. My favorite soap box is pointing out the Berg’s studies finding a high (80-90%) of CFS patients having an inherited coagulation condition have never been repeated. Having a single study results in those results being ignored because “they have not been repeated” — ignoring the fact that no one tried to repeat them…

My Role

What is my role? Basically, it is as a recovered former patient who remembers the pain and hurt that this condition caused. I looked at my strengths and weaknesses and realized that my best service to the community is simple:

  • Someone with a clear head who can read thru the literature, understand generally what the article actually says (i.e. cut thru researchers’ double speak). This arose from experience and training.
    • I started reading medical articles and presentations at 14 years old because I was one of 15 students from my grade level in one of the largest school districts in Canada for a special enrichment program, Berg Science Seminars.
    • I did an undergraduate and graduate degree in Statistics
    • My Master’s topic was working with the Justice Institute of BC looking at how various medical treatments influenced survival during medical transport.
    • I worked for many years as an Industrial Statistician and was a member of the American Statistical Association, as well as the American Mathematical Association, and a few other professional organizations.
  • My day-to-day job deals with very complex systems and data – literally world class Information Technology Systems including Microsoft, Amazon and Starbucks. I am one of those few people who doesn’t suffer from information or complexity saturation, rather, I sit down and slowly shift and re-shift the information to build out and then test a model as to cause and solution. I have been (and still am) successful in this area.  In July, 2017 I was the Edison Award Winner for the Starbucks Digital Platform Team.

My role is a citizen scientist modeler. It is “citizen” because I am not receiving any money for doing it. I have worked professionally as a scientist modeler.

My role is not:

  • CFS Life Coach
  • Action for getting more funding
  • Social Support
  • Treatment support

I could easily get involved with the above, but there are others who are more capable. My gifts are dealing with data and sketching out how the thousands of dots are connected. Taking these sketches and converting them into studies, treatment plans should be a role for the medical professionals. For example, Neem fits the model, but no one has done a clinical study on whether it is actually effective.

Bottom Line for Me

  • Continue to review studies, cutting thru the medical double talk
    • I am grateful for many readers who forward new studies to me for early review.
  • Continue to test and refine the model that seems to fit best against all of the data: microbiome x DNA/SNP interactions
    • Doing uBiome reviews help evolve the model
  • Continue to identify items which may help — based on applying the model to known literature.
    • Producing posts on these items with links to the research that I based it on (the keyword here is transparency)
    • Advising patients that these items should be discussed with their medical professionals before starting. I have blinkers on and have no idea if the same item may cause a different medical condition to get worse. Only your medical professional can determine if it is safe to try or not. I do not want to get sucked into time-consuming understanding of interactions, I would rather spend that time connecting more dots.


uBiome from a Hep Triggered CFS patient

Another uBiome result, as with other patients, low or no bifidobacterium and lactobacillus. Similar to most other patients, biodiversity was very high, 97%ile, with the usual many families at a very low (0.01 or 0.02) (trace) level compared to controls with the same families.

bb

Again, many rare ones show up

rare

Firmicutes to Bacteroidetes ratio was low 1.1: 1 instead of the normal 2.1:1. (about 1/3 have low ratios so far, and 2/3 have high ratios).

  • Akkermansia level is high (6.83) -seen in about 25% of the uBiome, the other 75% are low.
    • This subset of high patients also tend to be high in:
      • Alistipes, Bilophila, Intestinibacter,  Oscillospira, Intestinimonas,  Butyricimonas
      • This hints that 7 genus may be mutually beneficial to each other.

Notes on person: hepatitis triggered CFS over 20 years ago. Currently not doing any protocol.

The Low Amount of Abundance Bacteria Genus

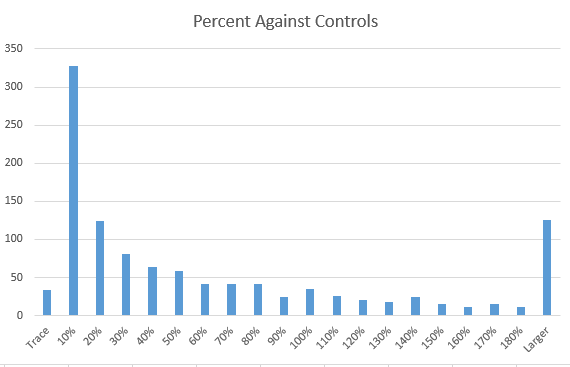
I have been recording the relative percentage (compare to controls) of different uBiome that I have reviewed. I took the numbers at the Genus (lowest) level, counted and plotted them.

spread

The expectation for a normal group of patients would be a bell/Normal-curve with the top of the bell being at 100. With CFS patients we find a large number of genus with a very low level compare to control.  In other words we have high biodiversity but it is very fragmented and made up of nominal populations. If the tests being applied to the microbiome was less sensitive than uBiomes, then a result of low biodiversity could be reported on the same sample because all of the trace, 10%, 20% may not be recorded.

Bottom Line

My best suggestion (especially since information on reducing Alistipes, Bilophila, Intestinibacter,  Oscillospira, Intestinimonas,  Butyricimonas is almost non-existent) is to discuss with their medical professionals the items on my “Cookbook Summary for the Brain Fogged“. The items are linked (eventually) back to the PubMed studies that provided dosage information.


uBiome with bioscreen results and an unwelcomed surprise

Another reader shared their uBiome results with bioscreen results (done the old fashion was of culturing bacteria). First thing is the classic “where’s the bifo and lacto!!” result seen with CFS/

cat

Looking at: Firmicute to Bacteriodetes ratio: 3.8 (double the typical ratio of 2.1), the volume of Bacteriodetes was the cause of the shift (50% of typical).

Over on Bioscreen, we see the rest of the normal story for CFS patients: Zero E.Coli and overgrowth (remember this is cultured, so only a few results will be shown — most gut bacteria cannot be cultured).

catl

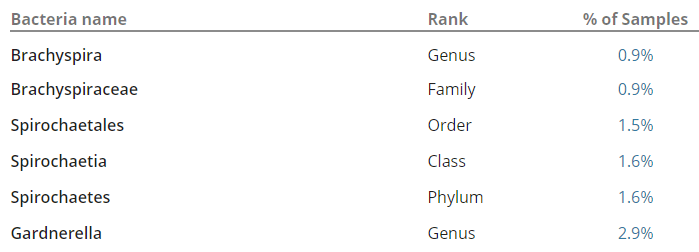
Going back to the uBiome results — we again see a fair number of rare bacteria appearing. There is no clear pattern beyond “a lot of rare ones appear”. For example, this is the first sample showing any of the Spirochaetia Phylum (The TOP level of bacteria tree). This family includes Borrelia burgdorferi, B. garinii, and B. afzelii, which cause Lyme disease.

cat3

Drill Down

Phylum Level

  • Lentisphaerae was 19.21x the average where as most CFS patients have zero
  • Tenericutes was 4.31x the average where as most CFS patients have zero

Class Level

  • Mollicutes (under Tenericutes) was 4.30x the average where as most CFS patients have zero. The best-known genus in the Mollicutes is Mycoplasma.

Order

Family

  • Victivallaceae (under Lentisphaerae) was 20.17x the average where as most CFS patients have zero

Genus

  • Victivallis (under Lentisphaerae) was 20.32x the average where as most CFS patients have none

Bottom Line

There was two major surprises in this uBiome — beyond seeing the usual CFS pattern:

  • Overgrowth of the class that contains mycoplasma – Mollicutes 
  • Overgrowth of the phylum that contains lyme bacteria – Spirochaetia

I do not know if one or the other have been tested for. The prescription antibiotics for both of these classes also overlap the generic CFS antibiotics and would likely reduce the overgrowth. My own preference (for myself), would be [with regular rotation]:

  • Tetracyclines: for example:
    • Doxycycline
    • Chlortetracycline.
    • Clomocycline.
    • Demeclocycline.
    • Lymecycline.
    • Meclocycline.
    • Metacycline.
    • Minocycline.
  • Macrolides:
    • azithromycin (brand name Zithromax),
    • clarithromycin (brand names Klacid and Klacid LA),
    • erythromycin (brand names Erymax, Erythrocin, Erythroped and Erythroped A),
    • spiramycin (no brand), and.
    • telithromycin (brand name Ketek).

Normally, lyme and mycoplasma are done by blood tests. If their “first cousins” and thriving in your gut, then the metabolites that they produce may be similar to those produce by lyme and mycoplasma — producing similar symptoms.

The lab results concluded “mild neutropenia” – WebMD cites for this condition

  • “Antibiotics for bacterial infections, if the underlying cause is an infection”
    • There appears evidence from the uBiome that there are atypical gut infections.

Again, this is not medical advise — just inferences from the data and the model that I am using. These inferences should be discussed with your knowledgeable medical professionals.

I will add to my backlog posts looking for herbs/spices etc that have been demonstrated effective for these two abnormalities.