What is comorbid with CFS/FM etc

Identified Sub Groups

From [2017] Study

  1. fibromyalgia, myofascial pain, multiple chemical hypersensitivity, sicca syndrome, epicondylitis, and thyroiditis
    1. “comprised mainly older women, with low educational level, unemployment, high levels of fatigue, and poor quality of life;”
  2. alterations of ligaments and subcutaneous tissue, hypovitaminosis D, psychopathology, ligamentous hyperlaxity, and endometriosis.
    1. comprised mainly older women, with low educational level, unemployment, high levels of fatigue, and poor quality of life;
  3. with hardly any comorbidities, comprising mainly younger women, university students or those already employed, with lower levels of fatigue, and better quality of life;
  4. poorly defined comorbidities;
  5. hypercholesterolemia.

Other Diagnosis

From 2000 Study

  • Self diagnosis of CFS [2013]
    • Sleep Disorder: 49.8% (especially obstructive sleep apnea syndrome)
    • Definite CFS: 23.3%
    • A psychiatric disorder was diagnosed in 45.2%; mostly mood and anxiety disorder.
  • Incidence of getting IBS:
    • chronic fatigue syndrome (CFS) –  92%;
    • fibromyalgia (FM) – 77%;
    • temporomandibular disorder (TMD) – 64%
  • Hyperacusis [2016]: Noise sensitivity
    • CFS – 3.2%
    • fibromyalgia – 4.2%
    • IBS  -4.8%
    • Anxiety Disorder – 47%
  • postural orthostatic tachycardia syndrome
    • CFS: 11% [2014]
    • Coeliac disease: 4% [2016]

Symptoms

From 2016 Australia Study according to the definition of CFS (Fukuda or  International Consensus Criteria). Percentage is given in ( )

Symptom Fukuda ICCa
Fatigue, n (%)
 Fatigued 162 (100.0) 171 (100.0)
 Postexertional malaise 68 (38.9) 171 (100.0)
 PENEe 25 (15.4) 171 (100.0)
Cognition, n (%)
 Confusion 52 (32.1) 69 (40.4)
 Disorientation 40 (24.7) 77 (45.0)
 Difficulty processing information 51 (31.5) 65 (38.0)
 Difficulty making decisions 53 (32.7) 66 (38.6)
 Slowed speech 46 (28.4) 75 (43.9)
 Difficulty reading 44 (27.2) 78 (45.6)
 Poor short-term memory 54 (33.3) 63 (36.8)
Pain, n (%)
 Headaches 51 (31.5) 64 (37.4)
 Muscle pain 53 (32.7) 65 (38.0)
 Joint pain 54 (33.3) 62 (36.3)
  Abdomen pain 42 (25.9) 71 (41.5)
 Chest pain 48 (29.6) 73 (42.7)
Sleep disturbances, n (%)
 Insomnia 46 (28.4) 69 (40.4)
 Prolonged sleep 51 (31.5) 57 (33.3)
 Reversed sleep 25 (15.4) 84 (49.1)
 Frequent awakenings 47 (29.1) 71 (41.5)
 Awakening earlier than expected 43 (26.5) 72 (42.1)
 Vivid dreams or nightmares 42 (25.9) 75 (43.9)
 Unrefreshed sleep 54 (33.3) 63 (36.8)
Sensory, perceptual, and motor disturbances, n (%)
 Inability to focus vision 47 (29.0) 69 (40.4)
 Sensitivitiesf 50 (30.9) 68 (39.8)
 Poor depth perception 30 (18.5) 78 (45.6)
 Muscle weakness 52 (32.1) 65 (38.0)
 Twitching 49 (30.3) 70 (40.9)
 Poor coordination 49 (30.3) 67 (39.2)
 Feeling unsteady on feet 44 (27.2) 70 (40.9)
Immune (infectious), n (%)
 Sore throat 45 (27.8) 73 (42.7)
 Tender lymph nodes 46 (28.4) 75 (43.9)
 Sinusitis 46 (28.4) 69 (40.4)
 Recurrent or persistent infections 46 (28.4) 71 (41.5)
Gastrointestinal and genitourinary, n (%)
 Nausea 44 (27.2) 73 (42.7)
 Abdominal pain 42 (25.9) 76 (44.4)
 Bloating 50 (30.9) 66 (38.6)
 Irritable bowelg 46 (28.4) 65 (38.0)
 Intolerancesh 45 (27.8) 68 (39.8)
 Urinary urgency or frequency 44 (27.2) 68 (39.8)
Cardiovascular, n (%)
 Orthostatic intolerancy 46 (28.4) 93 (54.4)
 Ataxiai 26 (16.1) 90 (52.6)
 Heart palpitations 42 (25.9) 65 (38.0)
 Light headedness 48 (29.6) 70 (40.9)
Respiratory, n (%)
 Air hunger 44 (27.2) 64 (37.4)
 Labored breathing 42 (25.9) 67 (39.2)
 Fatigue of chest muscles 50 (30.9) 68 (39.8)
Autonomic, n (%)
 Abnormal body temperature 41 (25.3) 66 (38.6)
 Fluctuating body temperature 48 (29.6) 67 (39.2)
 Sweating episodes 45 (27.8) 67 (39.2)
 Recurrent feverishness 43 (26.5) 75 (43.9)
 Cold extremities 45 (27.8) 72 (42.1)
 Intolerance of extremes temperature 50 (30.7) 67 (39.2)

Summary of Lipkin Analysis

As readers know, I have been on a deep dive into the results reported by Lipkin etc, doing one post a day on each of their findings over the last two weeks. The goal was to find patterns of what will help correct the shift. Below are my limited findings — based on very very limited published knowledge about each of the bacteria species.

Besides using PubMed, I have also obtain a copy of the 5 volume set Bergey’s manual of systematic bacteriology seeking additional fragments of knowledge.

In our review we found several weaknesses in this study:

  • Constipation-predominant irritable bowel syndrome(C-IBS) and plain IBS breakdowns should have been included. [See Parabacteroides Distasonis post]
  • Male and Female breakdowns should have been included. [See Parabacteroides Distasonis post]

My working hypothesis on the bacteria shift is simple, keeping with Osler’s Principles and Practice of Medicine. There is a risk of over-interpreting this data trying to find answers.

The over or under production of food is likely cause by an “island of stability” of other bacteria. My hope is that while we are attempting to  correct these bacteria that we destabilize this island and drift back to a normal situation. Everything is intertwained and cross-supported.

  • “Most of B. vulgatus [High], B. fragilis [High], B. ovatus and P. distasonis [Low] produced bacteriocins.[Natural antibiotics against other bacteria]”.  P.Distasonis appears to have a different bacteriocin profile — this the two high producers may be surpressing it.

High Bacteria

It appears that we can classify almost all of the HIGH bacteria to consumers of two food: Lactic Acid or Xylan.

Producers of Lactic Acid

  • Clostridium asparagiforme [HIGH] ” The organism produced acetate, lactate, and ethanol as the major products of glucose fermentation.” [2006]

Consumers of Lactic Acid

High d-lactic acid is a known characteristic for CFS. This is why I say to avoid lactic acid producing probiotics like Lactobacillus Acidophilus.

“The phylogenetic relationships of these nine lactate-utilizing, butyrate-producing strains based on their 16S rRNA sequences are summarized in Table 1. Four strains (from three individuals) are related to E. hallii, two (from two individuals) are A. caccae, and three (from two individuals) are distantly related to Clostridium indolis.” Lactate-Utilizing Bacteria, Isolated from Human Feces, That Produce Butyrate as a Major Fermentation Product [2004]

So bacteria that consume lactic acid are expected to be well fed and likely high. This is true for:

Consumers of Xylan

“Bacteroides Xylanisolvens, one of the species involved in breaking down xylan in the human gut, along with Bacteroides ovatus and ”Bacteroides fragilis” subspecies A.”[microbewiki]

So if we have levels of Xylan, we would expect well fed and likely high. This is true for:


“xylose increased the ileal butyric acid proportion, whereas arabinose increased the fecal butyric acid proportion. Moreover, chicory pectin increased the acetic acid proportion in both ileal digesta and feces.”[2014]

Bottom Line

I am really disappointed by their report. They reported only on a subgroup and appear not to have attempted to include in their scope, bacteria families reported prior (as far back as 1998!)

Lipkin Scope

  • Low
    • Pasteurellales [Order]
      • Lachnospiraceae [Family],
      • unclassified Bacillales[Family] and
      • Pasteurellaceae[Family]
    • Faecalibacterium [Genus],
    • Roseburia[Genus],
    • Coprococcus[Genus],
    • Gemella [Genus],
    • Dorea [Genus], and
    • Haemophilus [Genus]
  • High
    • Clostridiaceae [Family]
    • Clostridium [Genus],
    • Pseudoflavonifractor [Genus],
    • Anaerostipes [Genus]
    • Coprobacillus [Genus]

Prior Reports

These were not examined by them for some strange reason:

  • Lactobacillus (low) [1998]
  • Bifidobacteria (low) [1998]
  • E.Coli (low) [1998]
  • Klebsiella/Enterobacter (High) [1998]
  • Enterococcus (High) [1998]
  • Akkermansia (Low)
  • Firmicutes/Bacteroides ratio

These shifts have been repeatedly seen in uBiome and other lab results posted here. As a holder of a M.Sc. doing medical statistics — the design and approach appears very heavily suspect.

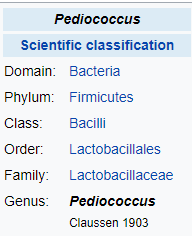
Pediococcus Pentosaceus Probiotics

This probiotic can be ordered in bulk from Korea.  It is often used in food processing. It’s Korean manufacture has some other rare probiotics which I will look at in the future. It is also available in Spain with Bifidobacterium longum.

Pediococcus is a Firmicute, which is the phylum that CFS/IBS/FM patients are too high in. This does not exclude it — but raises the bar to require known benefits.

Pedio

Microbewiki describes it as

“Pediococcus pentosaceus are categorized as a “lactic acid bacteria” because the end product of its metabolism is lactic acid [5]. Pediococcus pentosaceus, like most lactic acid bacteria, are anaerobic and ferment sugars. Since the end product of metabolism is a kind of acid, Pediococcus pentosaceus are acid tolerant[1]. They can be found in plant materials, ripened cheese, and a variety of processed meats[4]. Pediococcus pentosaceus is industrially important due to its ability as a starter culture to ferment foods such as various meats, vegetables, and cheeses[6]. Pediococcus pentosaceus bacteria is being cultured and researched for its ability to produce an antimicrobial agent (bacteriocins) as well its use in food preservation [6]…P. pentosaceus can produce an antimicrobial agent known as bacteriocins [3] “against several species of Lactobacillus, lactococcus, leuconostoc, pediococcus, staphylococcus, enterococcus, bacillus and listeria””

  • Adding another lactic acid produce is usually not desired because lactic acidosis is common with CFS/IBS/FM.
  • The antimicrobial agent it produces may be too widely targeted (kill the good and the bad).

The Known Science

Bottom Line

At this point of time, it is not recommended. It definitely has benefits in the food industry to stop spoilage. It has a very wide range of antibiotic action against both good and bad — and run a risk of doing more harm than good.


High ammonia levels in blood

A reader wrote: “I got some new results one that is really “exciting” is that I have very high Ammonia in my blood. What do you make of it? Normal range ends with 3, I have 7 Ammonia.”

According to WebMd, “An ammonia test measures the amount of ammonia in the blood. Most ammonia in the body forms when protein is broken down by bacteria in the intestines camera.gif. The liver camera.gif normally converts ammonia into urea, which is then eliminated in urine.”

The same protein intake will produce different amounts of ammonia in different people because what the protein is broken down to is determine by the bacteria.  Think of it this way, protein is like trees — people break them down and the outcomes are not the same: it may be houses, furniture or paper.  It depends on the people (bacteria) involved.

The best assumption is hyper-ammonia producing bacteria. [2004] identifies Klebsiella and Pseudomonas as ones. High Klebsiella was reported in the 1998 study of CFS Microbiome.

  • “The largest amounts of ammonia were generated by gram-negative anaerobes, clostridia, enterobacteria, and Bacillus spp.” [1980] High enterobacteria was also reported  in the 1998 study of CFS Microbiome.
  • “The effect of lactulose in reducing ammonia concentration is attributed to its role as a bacterial substrate in either increasing bacterial assimilation of ammonia or reducing deamination of nitrogenous compounds. The effect of low pH in reducing generation of ammonia appears to be part of a general reduction in bacterial metabolism.” [1978]

Bottom Line

High ammonia level in the blood has not been reported as a dominant CFS lab result  [1994]. It is unclear how often it is tested for when a CFS diagnosis is given.

It has been associated with Sjögren syndrome[2013] [2008]. Ammonia is a neurotoxin [2014] (thus may be a factor for brain fog) . This article cites some specific treatments (which likely would be helpful to many CFS patients):

  • “The nonabsorbed antibiotic rifaximin, when added to conventional therapy with lactulose, increases the rate of total reversal …” [2014]
  • “A combination of B. longum and FOS82 or a cocktail of four freeze-dried, nonurease-producing bacteria (Pediacoccus pentoseceus, Leuconostoc mesenteroides, Lactobacillus paracasei ssp. paracasei, and Lactobacillus plantarum) mixed with beta glucan, inulin, pectin, and resistant starch83 had similar effects. [2014]

Lactipro — having a cow looking for remission….

I reader asked me about Lactipro. This is an unusual probiotic for cattle, hence the title! Because it has not been tested on humans, I cannot advocate its use. I can research it potential impact if it is approved for human use somewhere in the world at some future time. I know of CFS patients who have order doxycycline from Vet Supply stores online because of frustration trying to get it prescribed, so I suspect some ‘dark-cure web‘ types will try it. So for their sake, I am doing this review.

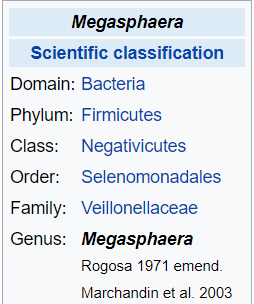
 Megasphaera elsdenii

From the manufacture web site, we read

“Effect of antimicrobials on Megasphaera elsdenii

Read about the effect of common antimicrobial agents on the growth and metabolism of Megasphaera elsdenii NCIMB 41125, a lactate utilising probiotic for ruminants.

Ability of Megasphaera elsdenii to prevent lactic acid buildup

Capability of Megasphaera elsdenii strain NCIMB 41125 and other probiotics to prevent accumulation of lactic acid in a rumen model.”

Since d-lactic acidosis is strongly associated with CFS, a probiotic that reduces lactic acid is ideal with my model.

The Science

From wikipedia we see that it is a Firmicutes, and CFS microbiome usually are high in firmicutes which means some caution and this may be a choice of the lesser of two evils.

There are some 240+ PubMed citations (most dealing with cattle)

Bottom Line

Don’t try it!  It is only found in humans suffering from gastrointestinal disorders. With my model CFS is a gastrointestinal disorder that may not manifest itself with gastrointestinal symptoms.

Further more, it pushes you further in the wrong direction.