Crohn’s Disease: Histamine Intolerance and CFS connection

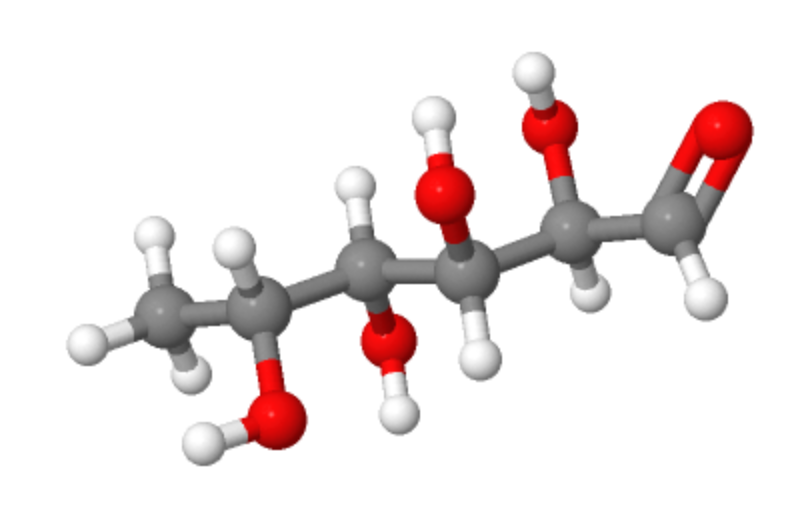
A recent article, J. Pickard et al., “Rapid fucosylation of intestinal epithelium sustains host–commensal symbiosis in sickness,” Nature, doi:10.1038/nature13823, 2014. with summary on TheScientist found that the sugar fucose  (yes, that is the correct spelling!) may play a major role. TheScientist article title says it well ‘Supporting the “Good” Gut Microbes During systemic infection, mice kick-start the production of a specific sugar to feed and protect the beneficial bacteria in their guts while fighting pathogenic strains.’

  • Chervonsky now wants to see how important this fucosylation pathway may be in humans. “About 20 percent of the population is missing the Fut2 gene, and this has been linked to Crohn’s disease.”
  • If you have done 23AndMe.com (which I would strongly recommend to any suffers from the above — it costs just $99 and allows you to see if new discoveries, like the Fut2 gene, is a factor for you). Fut2 is connected with Norovirus (aka Cruise Ship Sickness) resistance.

For the bio-Nerds:
“The fractionated fucoidan, especially the F1 fraction, strongly stimulated murine macrophages (Raw 264.7 cells), producing a considerable amount of nitric oxide (NO) and inducing expression of inducible NO synthase (iNOS), cyclooxygenase-2 (COX-2) and interleukin-10 (IL-10) transcripts by activation of nuclear factor-kappa B (NF-κB) and mitogen-activated protein kinases (MAPKs) pathways.” [2014] almost all of which are significant for CFS.

Screen Shot 2014-10-02 at 10.48.14 PM

We also found a 2001 study reports found that fucose “significantly and dose-dependently inhibited the histamine release induced”

Availability: Looking around on the internet, there appear to be sources for fucose — but at an unreasonable $100 for 1 g😦 – until you hit Alibaba, http://www.alibaba.com/showroom/fucose.html (Yes, I know it’s China — but the reality is that a lot of supplements you take are made there… at $1 for 2 lbs from some suppliers) There are more suppliers at http://www.chemicalregister.com/D-_+_-FUCOSE/Suppliers/pid93488.htm

  • Dosage – unknown I suspect < 1/8 teaspoon
  • Safety – no human trials that I could find. Material Safety Sheet provides little information.

WARNING: A reader has subsequently sent a variety of articles documenting that histamines are involved with suppressing TNF-alpha, thus a low histamine diet may make Crohn’s disease worst. 

My old Web Site from my 2nd CFS episode (2 years) and remission

This site was capture by a friend as a PDF and thus can be made available to you. Much of the information has been updated — but there are a lot of good links still in it — plus you can read my monthly logs as I worked thru CFS to remissions

  • idefx – my 1999-2001 trek to remission from CFS

Anatomy of a Multiple Chemical Sensitivty (MCS) Flare

I am coming out of a MCS flare at the moment. Many people have ongoing MCS flares, or MCS flares concurrent with multiple other symptoms.  Being in pretty much full remission (aka zero CFS symptoms), I believe that sharing my observations as to cause, model, symptoms and treatment may help some people.

Triggering Event

I am currently renovating our old home after it had been rented out for many years. For painting the exterior and interior, I had no MCS issues (defined as symptoms that persisted for more than 30 minutes after stopping an exposure). It was time to paint the interior and we hired someone to do the painting. They used a different brand of low VOC paint than what I had used for exterior and interior painting.

On my first visit to the house after the painting started, the fumes were thick because it had been raining and the windows had been kept closed. A slight headache which cleared after leaving. The next day, I awoke with a feeling of not wanting to go back to the house which I ascribed to not wishing to deal with the fumes.  I decided that if I open up the house quickly and worked outside, everything should be fine.

It was, running some errands etc gave me breaks. About 6 hrs later, I started to do some electrical wiring in the house but on a different floor with windows open — there was no smell of fumes that I could detect .. about 45 minutes later I knew something was wrong. Initial symptoms:

  • Stomach became very acidy
  • Loss of focus, easily distracted
  • Feeling off

Packed it in and headed home. Symptoms continue to worsen

  • Whole body aches and pain
  • Deterioration of cognitive ability
  • Very easy frustrated
  • Sore-raw throat
  • Fell asleep on the sofa about a hour later and slept very hard for 4 hours
  • Massive headaches across the front of the head
  • Lymph nodes swollen in the neck
  • Having mildly spice food cause a major over-reaction to the spice
    • Usually, I have no problem with Extreme Hot spices…
  • Sleep was disturbed — not just restless or difficult, but
    •  Many dreams that were very unsetting

On the first night after exposure, mild night-sweats returned, second night — major night sweats…

Treatment

I am on the path to recovery. First item comes from lab tests done prior to and two weeks after a MCS episode of a friend.  The marker for active coagulation went thru the roof (from high normal range (1.5 StdDev) to 7 standard deviation above the average — extremely high). Looking at the literature for allergies, you find that 30% of patients also have triggering of coagulation. This is definitely a part of MCS (and I suspect the main cause of many symptoms).

I proceeded with anticoagulation supplements:

  • Fibrin Breakers:
    • Turmeric
    • Piracetam
  • Antiplatelet
    •  Aspirin (and the above)

These are effective in treating reducing many of the symptoms. These will be ongoing supplements because it can take days or weeks for the increase in coagulation to reduce. This then takes me to the second part of the model.

The sore throat and lymph nodes are typical reaction to an infection. IMHO, MCS is the detection of certain chemical in the blood system that mimics chemicals produced by some past infections. The body thinks that it has detected the infection returning and proceeds to defend itself, this includes starting coagulation to slow the spread of the (apparent) infection.

A second aspect is that the chemicals are likely chemicals that the prior infections used to farm the gut bacteria — hence the stomach upset  as these chemicals triggers the residue amount of bad bacteria to go into overdrive! This response has the risk of the bad bacteria taking over — hence I proceeded to start pumping as many different types of probiotics into my stomach as I had available.

The third aspect is how to remove the chemicals from the body. There is a good chance that the concentration may actually be higher than that resulting from prior infections. I have learnt by experience that high fat food tends to reduce the concentration of these chemicals. One item, Olestra, is well documented as being the most effective substance to reduce PCB levels in the body.  On  a more humane front, brie and other cheeses will likely serve a similar function and is easy to test.

  • Have some and see if you are feeling better 15 minutes later. If the answer is yes, then you may wish to blow your diet and go on a cheese diet — or be real brave and go for an Olestra Potato Chip diet (which Walmart usually carry).

The symptoms are reducing, Brie is not bad medicine! But until the chemicals clear out of the body and the activated coagulation calms down,  it is working actively on reducing symptoms and encouraging the removal of the chemicals (and prevent re-exposure) on a day by day basis.

I recall from past literature that the reactivity of the body to an infection stays high for about a year and then slowly fades — which means that I need to minimize exposures to the same chemical for a year now that the body defense mechanism has been reactivated.

Please note that studies have found that sufficient chemicals can be capture by the moisture around the eye to provoke MCS. It is not a lung reaction — if the chemical gets into your system, even in very small quantity, it can provoke the immune system to believe that it is under attack…

Bacteria and Memory Issues

Readers know that my own experience was having a SPECT scan that was read as early Alzheimer’s Disease during my last flare. Remission of CFS resulted from aggressively altering bacteria. A reader just posted me a new research articles that rings true to me — because CFS has been associated with walking pneumonia in me for almost 40 years (before CFS was known). This was likely Chlamydophila pneumoniae in my case. 

J Alzheimers Dis. 2014 Sep 2. [Epub ahead of print]

Bacterial Infection and Alzheimer’s Disease: A Meta-Analysis.

Abstract

The possibility of an infectious etiology for Alzheimer’s disease (AD) has been repeatedly postulated over the past three decades. We provide the first meta-analysis to address the relationship between bacterial infection and AD. Studies examining the association between AD and spirochetal bacteria or Chlamydophila pneumoniae (Cpn) were identified through a systematic search of the databases MEDLINE, EMBASE, PubMed, and Google Scholar. Data combined from 25 relevant, primarily case-control studies demonstrated a statistically significant association between AD and detectable evidence of infection of either bacterial group. We found over a ten-fold increased occurrence of AD when there is detectable evidence of spirochetal infection (OR: 10.61; 95% CI: 3.38-33.29) and over a four-fold increased occurrence of AD in a conservative risk estimate (OR 4.45; 95% CI: 2.33-8.52). We found over a five-fold increased occurrence of AD with Cpn infection (OR 5.66; 95% CI: 1.83-17.51). This study shows a strongly positive association between bacterial infection and AD. Further detailed investigation of the role of bacterial infection is warranted.

An earlier study reported “After the first report on the presence of Chlamydia pneumoniae (Cpn) in brains of patients with AD appeared in 1998, this bacterium has most often been implicated in AD pathogenesis. However, while some studies demonstrate a clear association between Cpn infection and AD, others have failed to confirm these findings.” [2010]

The association issue failure is the classic medical tunnel vision — believing that a single infection is responsible for a single condition.  My model is that an infection by “farming the gut” will cause similar sets of bacteria overgrowth that will result in the same symptoms being reported. 

Interesting also, that antibiotics are known to slow Alzheimer’s disease. http://www.webmd.com/alzheimers/news/20031009/antibiotics-may-slow-alzheimers 

Interesting that they are also the ones that have been effective for CFS – 

“a three-month course of the antibiotics doxycycline and rifampin“


Memory Issues, Vitamin D and Chronic Fatigue Syndrome

I tend to view some of the processes involved with CFS to parallel (but are not identical) to Alzheimer’s Disease. Memory issues with CFS can remit with remission, AD has no remission.

Recently, the role of vitamin D with AD has had some research published (Journal Neurology, August 6, 2014). Low or very low Vitamin D levels double the risk of AD.  CFS research has found that the severity of symptoms increases with low levels of vitamin D and greatly reduce when patients are at the top of the recommended range (or slightly beyond).

One form of vitamin D, 1,25D (not normally tested for) appears to go up or down depending on severity of CFS symptoms.  By up, I mean very far above the normal range. When the lab did their first test of my 1,25 levels, it was so high they assumed a lab error. They repeated the test with the same result. With remission, I dropped down to the normal range of 1,25D.

A few years ago, there was a fad treatment, the Marshall Protocol, that promised remission if you pushed your Vitamin D level down to zero.  Bad idea. I know many people who tried it that are still addressing side-effects that arose during their attempt to do this protocol (under MD supervision).

And many many more!


How much, technically that needs to be done in consultation with your MD.  Most MDs will just want to get people into the bottom of the normal range. My physician wanted me to be near the top of the normal range. How much was I taking, around 20,000 IU of Vitamin D3 per day (as you get older, it takes more to maintain a level).


.