Neurology: Parkinson’s Disease

This is the second of a series of posts dealing with various forms of cognitive impairment that are often age related. My first post dealt with Alzheimer’s Disease and later posts on ALS. My personal suspicion is that a significant catalyst (if not actual cause) is the lost of microbiome as we age.

The Light Bulb Event

Almost a decade ago, I had a relapse of a condition that I had before and was sent for a SPECT scan. The radiologist suggested that it may be early onset Alzheimer’s. I was having problems with memory then, especially retaining recent memories. In 2017, for the same condition, a patient died and when their brain was examined, this study found

“Among the most remarkable pathological features of the case are focal areas of white matter loss, neurite beading, and neuritic pathology of axons in the white matter with axonal spheroids. Atypical neurons displaying aberrant sprouting processes in response to injury are observed throughout cortical gray and white matter. Abundant amyloid deposits identical to Alzheimer’s disease plaques with accompanying intracellular granular structures are observed as well. Neurofibrillary tangles are also present in the white matter of the frontal cortex, thalamus and basal ganglia. “

For myself, I went into remission. Memory and other issues faded — I am not 100% as strong in some cognitive aspects that I was prior, but to most people they cannot detect the remaining issues.

The condition that I had was successfully treated using a protocol that altered the microbiome. What if this was true for other similar conditions — especially the untreatable ones? Recent literature appears to support this.

  • “More recently, microbial dysbiosis has been associated with a number of brain pathologies, including autism spectrum disorder, Alzheimer’s disease (AD), Parkinson’s disease (PD), and amyotrophic lateral sclerosis (ALS), suggesting a direct or indirect communication between intestinal bacteria and the central nervous system (CNS). ” [2018]
  • “Gut microbial dysbiosis and alteration of microbial metabolites in Parkinson’s disease (PD) have been increasingly reported… Microbiota-targeted interventions, such as antibiotics, probiotics and fecal microbiota transplantation, have been shown to favorably affect host health.” [2018]
  • Progression of Parkinson’s disease is associated with gut dysbiosis: Two-year follow-up study.[2017]
  • “alterations in the gut microbiota composition in humans have also been linked to a variety of neuropsychiatric conditions, including depression, autism and Parkinson’s disease.” [2017]
  • “Alterations in bowel function, mainly constipation, often precede the onset of motor symptoms associated with PD“[2017]

CSF Proteins Dimension

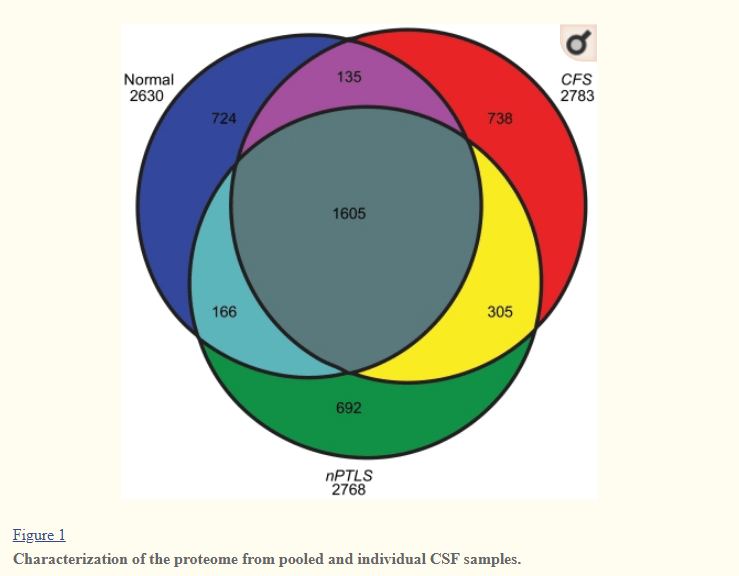
A 2011 Study found that Cerebrospinal Fluid Proteomes were different for my condition, a normal population and PTSD. These CFP’s are also heavily studied with Parkinson’s Disease ( 2009 Study) “proteins were identified that were able to differentiate atypical parkinsonian syndrome patients from healthy controls. Our study indicates that markers that may reflect neuronal function and/or plasticity, such as the amyloid precursor protein, and inflammatory markers may hold future promise as candidate biomarkers in parkinsonism.” [2017]  – both have novel proteins (i.e. proteins not seen in a healthy population).
d1

Working Hypothesis

My working hypothesis is that these CSF proteins are due to microbiome disruption. This disruption may not be a magic bacteria that causes it, but due to undersupply or oversupply of metabolites causing epigenetic changes in the bacteria resulting in these new proteins. Changes in Bacteroides fragilis is seen with both Parkinson’s Disease and Alzheimer’s disease.

  • “When stressed, overpopulated or pathogenically stimulated, B. fragilis releases a remarkably complex array of endotoxins and exotoxins (such as fagilysin), lipooligosaccahrides (LOS), lipopolysaccharide (LPS), including an extremely proinflammatory B. fragilis LPS (BF-LPS), microRNA-like sncRNA, and a wide variety of bacterial-derived amyloids (9–11, 56, 57, 64–66). ” [2018]

Hypothesis Tests

The hypothesis implies that there would distinctive shifts in bacteria seen with AD. What does the literature say?

  • “In addition, low counts of Bifidobacterium at year 0 were associated with worsening of hallucinations/delusions in 2 years. Similarly, low counts of B. fragilis at year 0 were associated with worsening of motivation/initiative in 2 years. The patients were evenly divided into the deteriorated and stable groups based on the degree of worsening of total UPDRS scores. The deteriorated group had lower counts of Bifidobacterium, B. fragilis, and Clostridium leptium than the stable group at year 0 but not at year 2, suggesting that the deteriorated group may demonstrate accelerated lowering of these bacteria at year 0.” [2017]
  • ” Among patients, independent signals were detected for catechol-O-methyltransferase-inhibitors (P = 4E-4), anticholinergics (P = 5E-3), and possibly carbidopa/levodopa (P = 0.05). We found significantly altered abundances of the Bifidobacteriaceae, Christensenellaceae, [Tissierellaceae], Lachnospiraceae, Lactobacillaceae, Pasteurellaceae, and Verrucomicrobiaceae families. Functional predictions revealed changes in numerous pathways, including the metabolism of plant-derived compounds and xenobiotics degradation… 13 operational taxonomic units (OTUs) had significantly altered abundances in PD vs. control samples, both using ANCOM (FDR<0.05) and Kruskal-Wallis tests (FDR<0.05).” [2017]
    • Prevotella was very high — Seven times that of controls.
  • “At the taxonomic level of genus, putative, “anti-inflammatory” butyrate-producing bacteria from the genera Blautia, Coprococcus, and Roseburia were significantly more abundant in feces of controls than PD patients. Bacteria from the genus Faecalibacterium were significantly more abundant in the mucosa of controls than PD. Putative, “proinflammatory” Proteobacteria of the genus Ralstonia were significantly more abundant in mucosa of PD than controls. “[2015]
  • “In particular, the abundance of Lachnospiraceae was reduced by 42.9% in patients with PD, whereas Bifidobacteriaceae was enriched in patients with PD. ” [2018]

Bottom Line

If you are a carer for someone with Parkinson’s Disease, you may wish to get a 16S analysis done ( for example uBiome.com – < $100) and upload the results to http://microbiomeprescription.com/. The suggestions there are based on hundreds of studies of what shifts different members of the microbiome. It’s a free site and the information is not available easily any wherelse.

  • “By applying metagenomic sequencing procedures, it is even possible to distinguish PD cases from healthy individuals at a very early disease stage by means of individually modified microbiota. ” [2018]

An example of getting suggestions is shown in this post.

I have updated the Parkinson’s Microbiome template on the site, i.e.

p2

Look at the suggestions and discuss them with your treating physician.

This is an education post to facilitate discussing this approach with your medical professionals. It is not medical advice for the treatment of any medical condition. Always consult with your medical professional before doing any  changes of diet, supplements or activity. Some items cites may interfere with prescription medicines.
 

Neurology – Sample Microbiome Analysis

In my last post, Dementia: Alzheimer’s Disease, I gave background on why microbiome alteration may moderate, perhaps reverse, the progression Alzheimer’s disease. In this post, I will show how you can get suggestions.

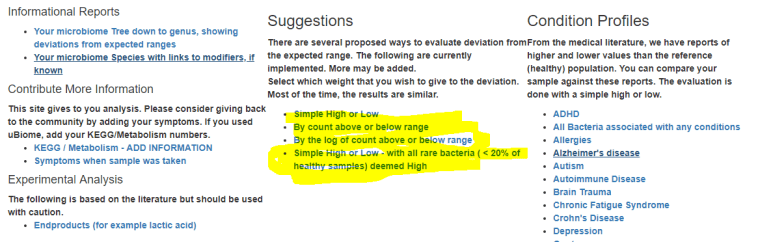
After uploading your 16S Microbiome (this can be done here), you will see displayed a link to analysis. Clicking it will take you to this page. Click any of the yellow items.

e1

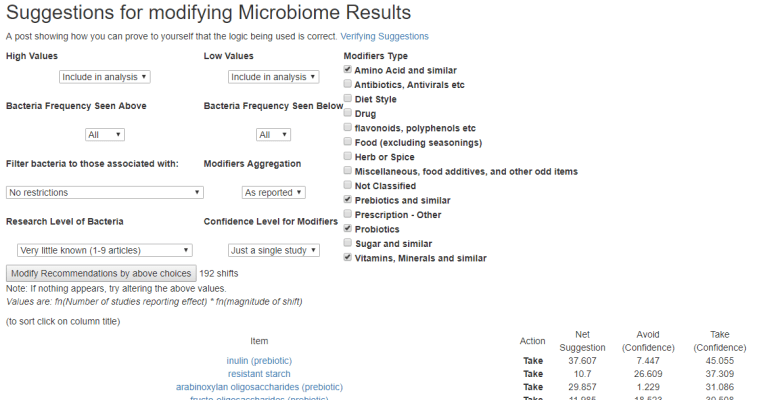
This will then go to the suggestions page.

e2

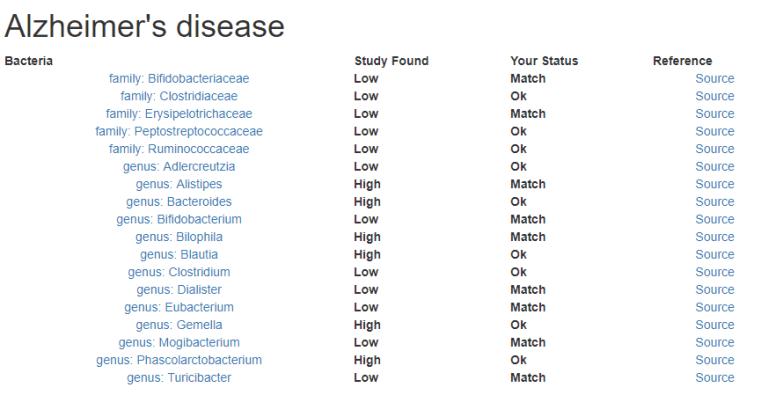
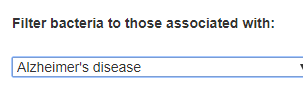
Instead of trying to change everything, we focus on the bacteria associated with Alzheimer’s. This is simple. Just pick Alzheimer’s

e3

Probiotics

Uncheck all items under Modifier Types except probiotics. There can be information overload with suggestions. Click the button “Modify Recommendation by above choices”

e4

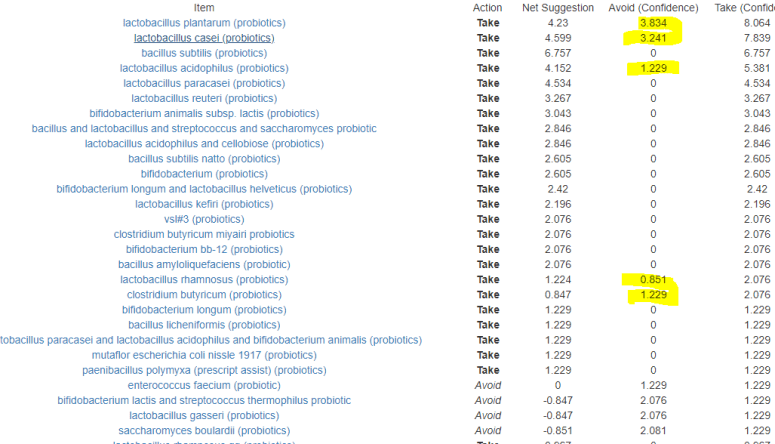
The yellow items above are items where it will make some of the bacteria better and some worst. I usually suggest avoiding all of them unless there are no other choices.

For probiotics, often they are mixtures — if all of them are on the Take list (without any yellow), then that is ideal.  For this example, if it contains any lactobacillus acidophilus then do not use it.

If you cannot find some of them, or any mixtures containing poor one,  you may wish to go to https://www.customprobiotics.com/ — this site sells single strain probiotics so you just order precisely what you. The price seems high but the actual cost per community forming units is very low. Some, like Mutaflor escherichia coli nissle 1917 (probiotics) is available in only some countries (Canada, Europe, Australia).

Vitamins

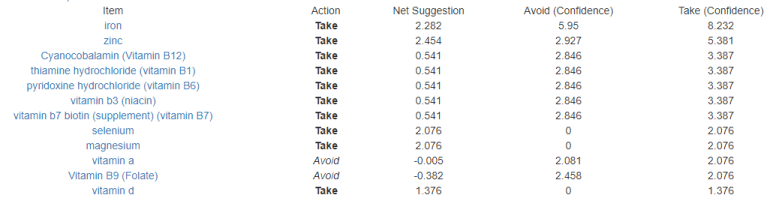
Some vitamins act as antibiotics when taken in sufficient dosage. For this sample, only vitamin D, magnesium and selenium are clear suggestions with no known negative aspects. Iron and selenium levels should be checked by your MD before starting. All of them should be at least at the average level according to the lab. For Vitamin D levels I prefer to be close to the top of the range – for older people, this may mean  15,000 IU/day to raise levels.

e5

Others

Explore the other choices. For the above sample, Mediterranean Diet was the strongest suggestion. Using raffinose(sugar beet)  for a sweetner.

Bottom Line

Interpret “Take” as increase or add to diet. “Avoid” as decrease or remove.  Each item should contribute — you do not need to do everything.

This is an education post to facilitate discussing this approach with your medical professionals. It is not medical advice for the treatment of any medical condition. Always consult with your medical professional before doing any  changes of diet, supplements or activity. Some items cites may interfere with prescription medicines.


Neurology: Alzheimer’s Disease

This is the first of a series of posts dealing with various forms of cognitive impairment that are often age related. The next posts deal with Parkinson’s and ALS. My personal suspicion is that a significant catalyst (if not actual cause) is the lost of microbiome as we age.

The Light Bulb Event

Almost a decade ago, I had a relapse of a condition that I had before and was sent for a SPECT scan. The radiologist suggested that it may be early onset Alzheimer’s. I was having problems with memory then, especially retaining recent memories. In 2017, for the same condition, a patient died and when their brain was examined, this study found

“Among the most remarkable pathological features of the case are focal areas of white matter loss, neurite beading, and neuritic pathology of axons in the white matter with axonal spheroids. Atypical neurons displaying aberrant sprouting processes in response to injury are observed throughout cortical gray and white matter. Abundant amyloid deposits identical to Alzheimer’s disease plaques with accompanying intracellular granular structures are observed as well. Neurofibrillary tangles are also present in the white matter of the frontal cortex, thalamus and basal ganglia. “

For myself, I went into remission. Memory and other issues faded — I am not 100% as strong in some cognitive aspects that I was prior, but to most people they cannot detect the remaining issues.

The condition that I had was successfully treated using a protocol that altered the microbiome. What if this was true for other similar conditions — especially the untreatable ones? Recent literature appears to support this.

  • “More recently, microbial dysbiosis has been associated with a number of brain pathologies, including autism spectrum disorder, Alzheimer’s disease (AD), Parkinson’s disease (PD), and amyotrophic lateral sclerosis (ALS), suggesting a direct or indirect communication between intestinal bacteria and the central nervous system (CNS). ” [2018]
  • “It seems that, inflammatory-infectious hypothesis of AD, with the great role of the gut microbiome, starts to gently push into the shadow the amyloid cascade hypothesis that has dominated for decades.” [2018]
  • “The first indication of a potential mechanistic link between the pathobiology of the human gastrointestinal (GI)-tract microbiome and its contribution to the pathogenetic mechanisms of sporadic Alzheimer’s disease (AD) came a scant 4 years ago (1).”[2018] — I suspected this much earlier 😉

CSF Proteins Dimension

A 2011 Study found that Cerebrospinal Fluid Proteomes were different for my condition, a normal population and PTSD. These CFP’s are also heavily studied with Alzheimer’s Disease (2016 study), “We report strong evidence of previously reported CSF proteins and several novel CSF proteins specifically associated with amyloid pathology or neuronal injury and tau hyperphosphorylation.” [2018] – both have novel proteins (i.e. proteins not seen in a healthy population).

d1

Working Hypothesis

My working hypothesis is that these CSF proteins are due to microbiome disruption. This disruption may not be a magic bacteria that causes it, but due to undersupply or oversupply of metabolites causing epigenetic changes in the bacteria resulting in these new proteins.

  • “When stressed, overpopulated or pathogenically stimulated, B. fragilis releases a remarkably complex array of endotoxins and exotoxins (such as fagilysin), lipooligosaccahrides (LOS), lipopolysaccharide (LPS), including an extremely proinflammatory B. fragilis LPS (BF-LPS), microRNA-like sncRNA, and a wide variety of bacterial-derived amyloids (9–11, 56, 57, 64–66). ” [2018]

Hypothesis Tests

The hypothesis implies that there would distinctive shifts in bacteria seen with AD. What does the literature say?

  • “the most enriched bacteria at genus level, the proportions of Acetobacter and Lactobacillus decreased dramatically. Acetate was the most abundant SCFA derived from the dysregulated microbiota and markedly downregulated in AD Drosophila.” [2018]
  • “We identified phylum- through genus-wide differences in bacterial abundance including decreased Firmicutes, increased Bacteroidetes, and decreased Bifidobacterium in the microbiome of AD participants. Furthermore, we observed correlations between levels of differentially abundant genera and cerebrospinal fluid (CSF) biomarkers of AD. ” [2017]
  • “Also, a very intriguing discovery in AD is that the Mediterranean diet (MeDi), containing an unusually large quantity of Lactobacilli, is very effective in preventing AD… it is our opinion that the reduction of blood ammonia levels by Lactobacilli in MeDi is the therapeutic agent of MeDi for AD. ” [2018]
  • Lactobacilli and bifidobacteria ameliorate memory and learning deficits and oxidative stress in β-amyloid (1-42) injected rats.[2018]
  • Therapeutic potential of Bifidobacterium breve strain A1 for preventing cognitive impairment in Alzheimer’s disease.[2017]
    • “These findings indicate that AD pathology might not only affect brain function directly, but also exacerbate cognitive deficits through reducing the level of SCFAs via alterations of gut microbiota induced by intestinal amyloid deposition. Our data may support a role of gut microbiota, and suggest a novel route for therapeutic intervention in AD.”
  • “Clinical studies have shown that, in cognitively impaired elderly patients with brain amyloidosis, there is lower abundance in the gut of E. rectale and B. fragilis, two bacterial species which have an anti-inflammatory activity, versus a greater amount of pro-inflammatory genera such as Escherichia/Shigella. ” [2018]
  • “Our findings suggest an increase in bacterial populations in Alzheimer brain tissue compared with normal.” [2017]
  • “We concluded that the cognitive and biochemical indications in the patients with severe AD are insensitive to the probiotic supplementation.” [2018]

Bottom Line

If you are a carer for someone with Alzheimer’s Disease, you may wish to get a 16S analysis done ( for example uBiome.com – < $100) and upload the results to http://microbiomeprescription.com/. The suggestions there are based on hundreds of studies of what shifts different members of the microbiome. It’s a free site and the information is not available easily any wherelse.

An example of getting suggestions is shown in this post.


I have updated the Alzheimer’s Microbiome template, i.e.

d3

Look at the suggestions and discuss them with your treating physician.

This is an education post to facilitate discussing this approach with your medical professionals. It is not medical advice for the treatment of any medical condition. Always consult with your medical professional before doing any  changes of diet, supplements or activity. Some items cites may interfere with prescription medicines.
 

Validating Suggestions

A reader found a bug for low levels of bacteria. To empower readers to be able to check the basic logic being used, I created this post (after fixing the above bug caused by a misplaced minus sign).

Sometime people ask “Are the suggestions reasonable?”

  1. Go to http://microbiomeprescription.com/labs/definition?key=L
  2. Change one to HIGH i.e.  Burkholderiaceae [family]
  3. Click on it to see what impacts it, http://microbiomeprescription.com/Library/Details?taxon=119060&taxname=Burkholderiaceae%20[family]
    v1
  4.  Click on Submit
  5. Examine the suggestions, do they agree?
    v2
  6. Repeat with a LOW amount — do they agree

v3

Bottom Line

One of the goals of the rework was to consolidate the suggestions logic into a single piece of code that will be used everywhere. It means that quality assurance becomes less manpower intensive.


Major Refactor is ready for testing and comments

The analysis site for 16s microbiome results (ubiome, thryve, etc) http://microbiomeprescription.com/ has been revised to improve usability and to give more options.

Sample Selection Page

This has been de-cluttered

s1

Ability To Edit some Meta Data

Clicking on Edit or Remove a sample.

  • Some Json files did not include a date, so you may manually correct it.
  • There are a few non-US medical professionals who uses this site, so support for adding a person name
  • I have had requests to remove samples — this makes it easy to do. You must enter the email as a validation step (to stop accidental removals)

s13

New Analysis Page

This page is rich in options, but to get there you must have selected a specific gut sample. If you uploaded ear samples, this page will not be available.

s3

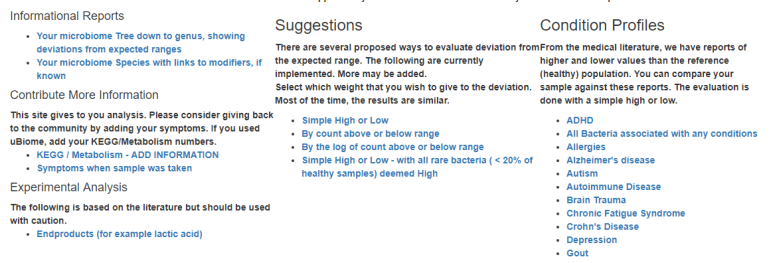
Informational Reports

Microbiome Tree

This shows the hierarchy of bacteria you have with the ration to the reference range. High values are in Red.  This allows you to see exactly where shifts are happening.  For example we see Veillonellaceae are high — but this is because two specific genus are high in this family.

s4

Species

Your species are usually not shown on the ubiome report but is in the data. This lists the species. Each species is hyperlink to information on modifiers.

s5

Example of a report

s6

Contribute More Information

This allows you to add additional information — symptoms when you did your sample, the KEGG information from ubiome reports.

Experimental Analysis

This is experimental — it has resulted in some strong associations with the symptom explorers.

Suggestions

People can argue endlessly about what is significant or insignificant. To save the arguments, I give 4 different ways to evaluate deviations. I have done the 4 options on the same data below.

When you click thru you will see suggestions with the new filtering options:

Simple High Low

s7

Count Above or Below

So an item that is a little high or low is not given as much weight as an item that is very high or low.

s8

Log of Count

As above, but by taking the log, the severe impacts are scaled down.

s9

Simple Count with Rare Bacteria deemed to be Highs

For rare bacteria, we often do not know if it is bad or good. We assume that it may be bad.

s10

Suggestions Filter

The filter has been updated to give better control (less noise) of suggestions. The default values are expected to work for most people.

s11

Condition Profiles

This is informational and definitely not diagnostic. When you click on one, you will see how well your shift matches those reported in studies.

s12

Bottom Line

I suspect that there are bugs, so please email me at ken/at/lassesen/dot/com when you find them. I have taken the next three days off to respond to bugs quickly.