Fibre/FODMAP and CFS/IBS/FM

In researching my last post on Psyllium fiber, I was surprised to find no known positive effects. Some of my readers asked about other fiber. Rather than piecemeal a series of post — I thought I should research the area and find what is actually demonstrated and not what has evolved in alternative health beliefs.

“In an attempt to bridge this “fiber gap,” many consumers are turning to fiber supplements, which are typically isolated from a single source. Fiber supplements cannot be presumed to provide the health benefits that are associated with dietary fiber from whole foods. Of the fiber supplements on the market today, only a minority possess the physical characteristics that underlie the mechanisms driving clinically meaningful health benefits…. This emphasizes the importance of recognizing that not all marketed fiber supplements will provide the clinical efficacy of the original raw fiber“[2015]

Conditions Related Studies

NOTE: I view FM/IBS/CFS to be very similar dysfunction of the microbiome with results for one being applicable to all.

  • “What increases inflammation are hypercaloric Western-style diets, characterized by high salt, animal fat, red meat, sugar-sweetened drinks, fried food, low fiber, and lack of physical exercise.” [2015] –
    • This is likely the root of recommending fiber supplements — but there is a major difference between pure fiber and high fiber food (which contains many other things — like complex sugars (not the white sugar we add to tea).
    • “Conversely, exercise and low-calorie diets based on the assumption of vegetables, fruit, legumes, fish, prebiotics, and probiotics act on nuclear receptors and enzymes that upregulate oxidative metabolism, downregulate the synthesis of proinflammatory molecules, and restore or maintain a healthy symbiotic gut microbiota.”
  • “Of the CFS patients, 23% smoked, 32% had an unhealthy BMI, and none had an unhealthy alcohol intake. A majority had an unhealthy food intake: 70% had unhealthy fat, fruit and vegetable intake, and 95% had unhealthy fibre intake.” [2009]
  • On Fibromyalgia [2016]
    • “A daily or almost-daily consumption of fruit and vegetables and a moderate consumption of fish (2 to 5 servings per week) were associated with higher scores in mental health (P<0.001, P<0.05, and P<0.001, respectively) and lower levels of depression (P<0.001, P<0.01, and P<0.01, respectively).”
    • “A daily or almost-daily consumption of vegetables and a moderate consumption of dairy products and fish were associated with higher levels of optimism (P<0.05, P<0.05, and P<0.001, respectively).”
    • “A daily or almost-daily consumption of cured meats and sweetened beverages were associated with higher levels of depression and lower levels of optimism, respectively (both P<0.05).”
    • “However, intake of foods rich in polyphenols was associated with lower numbers of tender points (coffee, r = – 0.346; pear, r = – 0.331) and better quality of life (red fruits, r = – 0.342; dark chocolate, r = – 0.404) in the fibromyalgic group.” [2016]
  • “Dietary fiber that is intrinsic and intact in fiber-rich foods (eg, fruits, vegetables, legumes, whole grains) is widely recognized to have beneficial effects on health when consumed at recommended levels (25 g/d for adult women, 38 g/d for adult men). Most (90%) of the US population does not consume this level of dietary fiber, averaging only 15 g/d.” [2015]  Refined items with NO CLINICALLY demonstrated health benefits:
    • Wheat Bran (wheat)
    • Wheat Dextrin (treated wheat)
    • Inulin (Chicory root)
    • Methylcellulose (wood pulp)
    • Partially Hydrolyzed Guar Gum (Guarn beans)
    • Beta-Glucan (Oats, Barley)
  • “A high fibre intake (> 25-30 g/day) based on a variety of food sources (fruit, vegetable, legumes, cereals) is the only way to avoid many of the disorders mentioned.” [2002]
  • “FODMAPs (fermentable oligosaccharides, disaccharides, monosaccharides and polyols) have been shown to trigger gastrointestinal symptoms in patients with IBS.” [2014] – whether this is good (microbiome change) or bad (uncomfortable), seem unclear. Digging further…
    • “Certain food items trigger the symptoms experienced by IBS patients, including those rich in fermentable oligo-, di- and monosaccharides, and polyols (FODMAPs). ” [2014]
    • “a diet low in FODMAPs effectively reduced functional gastrointestinal symptoms[ in IBS]. [2014]
    • “Perceived intolerance to high FODMAP foods and low FODMAP foods were both statistically significantly associated with exposure to Giardia infection [resulting in IBS].” [2015]
    • Managing irritable bowel syndrome: The low-FODMAP diet [2016].
    • Efficacy of the low FODMAP diet for treating irritable bowel syndrome: the evidence to date [2016].
    • “Histamine, a measure of immune activation, was reduced eightfold in the low FODMAP [IBS] group (p<0.05).” [2016]
    • “The daily total consumption (mean±s.e.m. values) of fruits and vegetables rich in FODMAPs (fermentable oligosaccharides, disaccharides, monosaccharides and polyols) decreased significantly from 16.2±5.3 g before receiving dietary guidance to 9.2±3.2 g after receiving dietary guidance (P=0.02)…The densities of the large intestinal endocrine cells tend to normalize following dietary guidance that may have contributed to the improvement of the patients with IBS symptoms.” [2016] – going FODMAP appears to be a poor decision.

Microbiome Studies

  • ” Low FODMAP diet increased Actinobacteria richness and diversity, and high FODMAP diet decreased the relative abundance of bacteria involved in gas consumption.”[2016]
  • ” The low FODMAP diet was associated with higher faecal pH (7.37 vs. 7.16 ), similar short-chain fatty acid concentrations, greater microbial diversity and reduced total bacterial abundance (9.63 vs. 9.83 ) compared with the Australian diet.” [2015]

Bottom Line

  • You may wish to print off this list. or try this iphone application or android app
    • Remember — we do NOT know if all of fermentable oligosaccharides, disaccharides, monosaccharides and polyols are to be avoided. This is a direction — not a detailed route.
  • Do not bother spending money on fibre supplements — their only effect is shrinking your wallet.
  • Less (ideally no) refined and prepared food — fruit, legumes and vegetables — especially raw!

Filtered Table

The following table was created from two lists I found on the web – high fiber foods excluding high FODMAP items. This is to help the brain fogged.



Psyllium fiber impact on the microbiome

A reader asked me about psyllium fiber. I find that I always want to check “common medical beliefs” against PubMed.com — very often what was believed 10 years ago has been shown to be incorrect.

  • Psyllium Fiber Reduces Abdominal Pain in Children With Irritable Bowel Syndrome in a Randomized, Double-Blind Trial [2016]
  • Psyllium Fiber Does Not Alter Gut Microbiome Composition in Children With Irritable Bowel Syndrome (IBS) [2016]

  • “In general, high doses (≥7 g) of wheat bran, inulin, and psyllium tend to delay gastric emptying, whereas lower doses do not show a significant effect…” [2013]
    • “treatment with dried plums (prunes, 6 g/day fiber) compared with psyllium (6 g/day fiber) in 40 patients (99). Dried plums not only contain fiber but also sorbitol and fructans, non-absorbable carbohydrates that, when fermented by colonic bacteria, create an osmotic load that can dramatically alter stool frequency and consistency (100). Treatment with dried plums resulted in a greater improvement in constipation symptoms as reflected by a significant increase in the number of complete spontaneous bowel movements and in stool consistency (softer stools) when compared to treatment with psyllium”
    • “The difference between psyllium and placebo, however, was no longer significant at 3 months. Bran provided benefits over placebo only at 3 months. Over 60% of subjects randomized to psyllium or bran reported moderate adverse events, the most common of which were constipation and diarrhea.”
    • “an often-cited patient survey of 100 IBS patients found that 55% felt worse and only 10% felt better on bran (105).”
  • “Less fermentable psyllium fiber was shown to shift the fermentation of high-amylase–resistant starch toward the distal colon in rats (22)….Psyllium fiber supplementation (7–14 g/d for 3 mo) to obese individuals led to no changes in the inflammatory markers (66)…a diet supplemented with psyllium to a final total fiber concentration of ∼27 g/d were found to similarly decrease the amount of C-reactive protein. The effect was greater in lean normotensive subjects than in obese hypertensive subjects (69).”. [2013]

We are talking about 1 ounce by weight. i.e. 3 bottles of below a month
now-05966-5

    • Bottom Line

    • Taking psyllium has no documented benefit for IBS or CFS. It does not alter the microbiome and had a significant (60%) risk of moderate adverse effect.
    • Consider dry plums instead!! or any high fiber fruit!

Penicillin and amoxicillin and the Microbiome

The next family of antibiotics that I found studies on was penicillin, typically amoxicillin. With many older theories of CFS, this family of antibiotics was believed to encourage the growth of bacteria suspected to cause CFS. Often you will read of bad reactions of CFS patients to this family of antibiotics.  There appear to be some “truth” to this — but in a negative sense — it does not encourage the growth — rather it reduces already low level of two major families of bacteria  seen with CFS patients…  so yes, it will likely make most CFS patients worst.

“Oral amoxicillin exposure caused marked shifts in microbiome composition that lasted approximately 30 days on average and were observed for more than 2 months in some of the treated individuals .” [2016]

  • “The use of amoxicillin also influenced the intestinal microbiota, significantly decreasing the CFU of Bifidobacterium spp. and Lactobacillus spp./g of feces.” [2005]

The first study was interesting Prospective randomized controlled study on the effects of Saccharomyces boulardii CNCM I-745 andamoxicillin-clavulanate or the combination on the gut microbiota of healthy volunteers[2016].

kgmi_a_1267890_f0003_oc

Unfortunately the rest of the images in this study were well above the cognitive level of most CFS patients.

Microbial diversity in individuals and their household contacts following typical antibiotic courses [2016]. “As few as 3 days of treatment with the most commonly prescribed antibiotics can result in sustained reductions in microbiota diversity,” Again, this article have complex charts.

Effects of Gut Microbiota Manipulation by Antibiotics on Host Metabolism in Obese Humans: A Randomized Double-Blind Placebo-Controlled Trial [2016].

Long-term changes in human colonic Bifidobacterium populations induced by a 5-day oral amoxicillin-clavulanic acid treatment [2012]. is of special interest becasue bifidobacterium is low with CFS patients. This antibiotic makes it worst!

bifido

I have created a page that processes existing literature and produces a list of suggestions on what may counteract the antibiotic shift. The page is [here]

Macrolide impact on the Microbiome

In this post, I will look at the impact of macrolides on microbiome. Macrolides are used by Cecile Jadin in her protocol (Notice: I used her protocol as a basis for 2 remissions — I may be bias!).

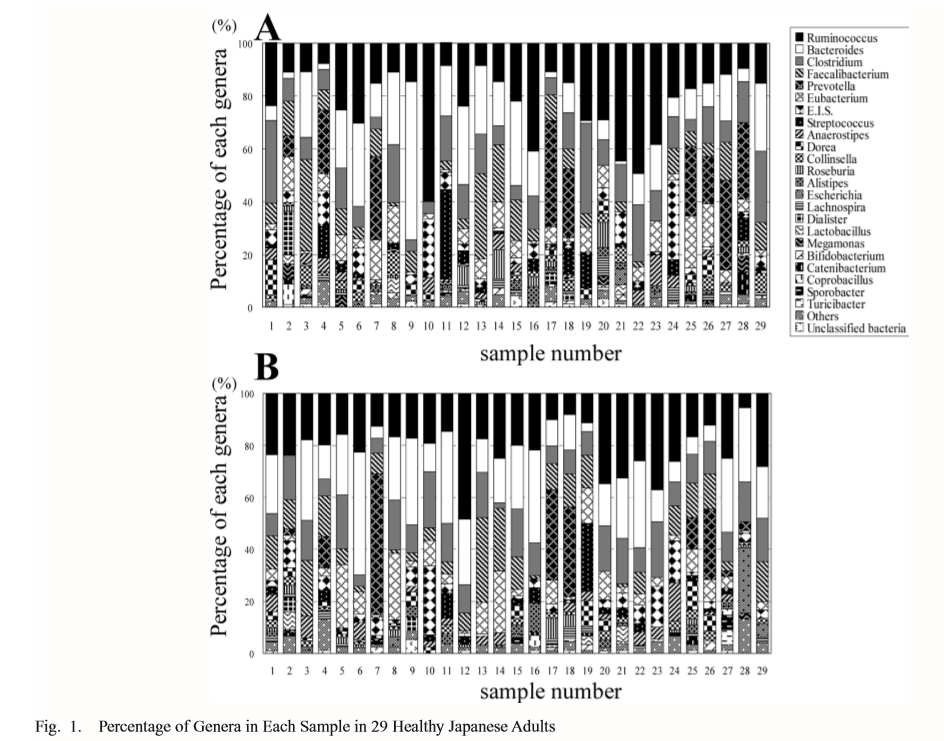
This [2011] article is the basis of this post. The first thing is to note that with these 29 healthy same-ethnic group people, the relative numbers vary greatly!!!!

japan

The is no “normal” microbiome — it is very very individualistic and change over time.

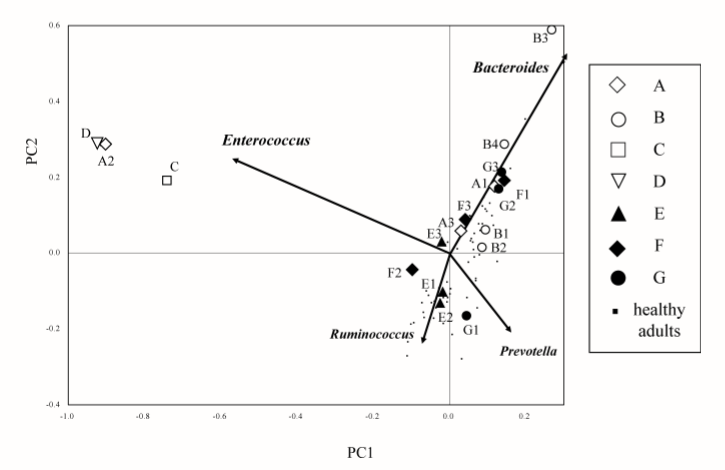
When a macrolide was give, they saw shifts in different directions (the E-G solid colors below)

japan1

” On the other hand, macrolide treatment showed the effects depending on the cases. E and G samples located just within the area which healthy adult samples distribute, despite antibiotic administration. However, F samples were spotted on the left lower of the PCA map.” – In other words, the impact will vary from person to person.

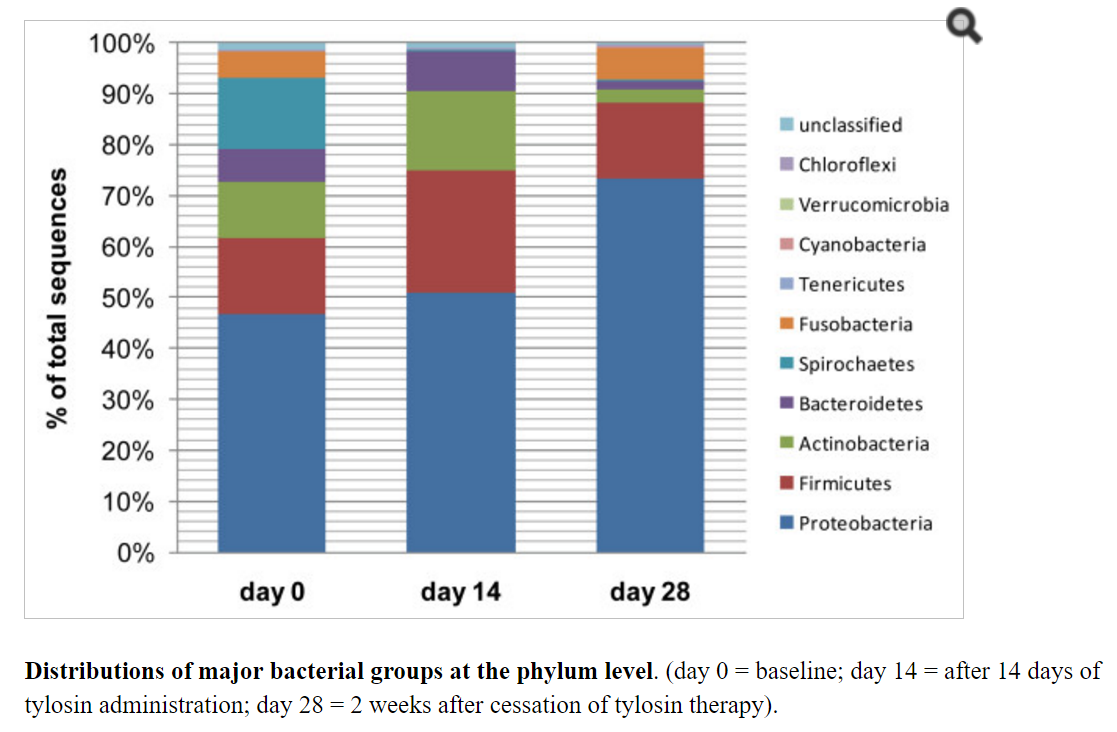
Another study [2009] show the trend over a month – not some phylum disappear completely (Spirochaetes) and other disappeared and re-appeared (Fusobacteria)

trend


Small Intestine Bacterial Overgrowth (SIBO)

This issue often comes up in discussions with CFS/FM/IBS

  • “Recent research shows that patients with CFS have marked alterations in microbial flora, including lowered levels of bifidobacteria and small intestinal bacterial overgrowth (SIBO).” [2003]
  • “a considerable proportion of patients with fibromyalgia experience gastrointestinal symptoms that are commonly overlooked in the studies that are not specifically dedicated to evaluate these manifestations.” [2015]
  • “Recent investigations have shown that bacterial overgrowth of the small intestine is associated with a number of functional somatic disorders, including irritable bowel syndrome (IBS), fibromyalgia, and chronic fatigue syndrome.” [2002]

The model that I use is based on a shift of the microbiome — some overgrowth and some undergrowth. SIBO is a subset of this definition.

According to wikipedia, there are multiple methods of diagnosis — the basis of these methods is abnormal results with “some physicians suggest that if the suspicion of bacterial overgrowth is high enough, the best diagnostic test is a trial of treatment. If the symptoms improve, an empiric diagnosis of bacterial overgrowth can be made.[39]“

Under treatment: ” However, if the condition recurs, antibiotics can be given in a cyclical fashion in order to prevent tolerance. For example, antibiotics may be given for a week, followed by three weeks off antibiotics, followed by another week of treatment. Alternatively, the choice of antibiotic used can be cycled.[39]” — the cycling of antibiotic choices is a regular part of Jadin’s protocol for CFS.

Latest from PubMed

  • For rifaximin, “The overall eradication rate according to intention-to-treat analysis was 70.8%…The overall rate of adverse events was 4.6%… improvement or resolution of symptoms in patients with eradicated SIBO was found to be 67.7%”[2017]
    • “Although the rifaximin group showed a greater percentage of global symptom improvement, this was limited to bloating, as scores for abdominal pain, diarrhea, and constipation did not improve significantly.”[2007]
  • “SIBO was found to be associated with deep vein thrombosis (DVT).” [2016] — which implies coagulation may be associated with SIBO (i.e. thick blood).

Bottom Line

SIBO is a common condition with vague diagnosis criteria. Often the treatment and diagnosis is for one particular group of bacteria — for example Hydrogen Sulfide. A MD may tell the patient, your SIBO is resolved and the reality is that only the Hydrogen Sulfide producing bacteria has been reduced, the rest remain active — creating symptoms of FM, CFS, etc.

In short, SIBO — both tests and treatment are a part of the solution to CFS/FM/IBS but is not the full answer and likely, IMHO, not a major part of the answer. False positives and negatives are common with common tests.

On the PLUS SIDE — as with chronic lyme, SIBO can be a justification(defense) for a MD to prescribe antibiotics. Prescribing antibiotics for CFS or FM is not politically acceptable in most countries.